Nasolabial folds · what the trials actually did
Your smile lines are a seam, not a wrinkle.
For women who want the fold softened, not their face filled.
Every treatment graded on its own trials, from a syringe to a facelift, sorted by the cause it actually reaches.
Sound familiar?
- The line from your nose to your mouth stays long after the smile has gone.
- Photographs taken from slightly below show a deeper fold than your mirror does.
- You would like it softer, but you have seen folds filled flat and want nothing like them.
Start here
What a nasolabial fold actually is
A seam between two tissue architectures — loose cheek fat with long septa on one side, tight muscle-anchored lip skin on the other — present in every smile at every age. It deepens at rest as the cheek above it descends and deflates.
What a nasolabial fold actually is
A seam between two tissue architectures — loose cheek fat with long septa on one side, tight muscle-anchored lip skin on the other — present in every smile at every age. It deepens at rest as the cheek above it descends and deflates.
The nasolabial fold runs from the wing of the nose to the corner of the mouth and marks a change in construction. Lateral to it, the cheek is built of fat compartments threaded by long fibrous septa; medial to it, the upper lip is a condensed, tightly septated layer where the zygomaticus and lip-elevator muscles insert directly into the skin. Histological mapping of donor faces found the fold sitting exactly on the border between the two, with no ligament required to explain it (morphological study). That is why it exists in every child's smile: the lip side lifts and the cheek side does not, and the skin folds at the seam.
What ages is the fold at rest. The cheek's fat compartments deflate and the malar fat pad migrates downward, heaping tissue against the anchored seam (cheek fat compartments); the maxilla and the rim of the pyriform aperture resorb, so the top of the fold loses its bony shelf (Mendelson & Wong); and the skin thins and loses recoil. Anatomists now sort folds by which of these dominates — fat-pad, bone-retrusion, skin, muscular and hybrid types — because each wants a different treatment (anatomical review).
Who gets deep folds, and when
Everyone has the crease; most people notice the resting fold in their forties. Smoking, sun, and losing more than a tenth of body weight after 45 deepen it measurably; bariatric-scale weight loss ages the midface about five years.
Who gets deep folds, and when
Everyone has the crease; most people notice the resting fold in their forties. Smoking, sun, and losing more than a tenth of body weight after 45 deepen it measurably; bariatric-scale weight loss ages the midface about five years.
The crease is universal; the resting fold is a decade-by-decade story, usually first noticed in the forties in a photograph taken from below. Identical-twin comparisons put smoking among the strongest modifiable factors, with the smoking twin scoring worse for nasolabial folds alongside jowls and lip lines (twin study). Weight is the other lever: volumetric imaging shows deep facial fat emptying with weight loss, and people who lost more than 10% of their weight after 45 showed a marked accentuation of nasolabial folds and cheek grooves (ASPS); after bariatric-scale loss, blinded raters judged faces about five years older than their age, with deepened folds and midface descent (systematic review). Sun and side-sleeping do the rest.
Why the fold resists being "lifted"
The seam is stitched to muscle, so pulling the cheek sideways or upward moves the cheek, not the fold: a 77-patient imaging study found cheek filler does not shift the fold’s skin, and a 16-study review found facelift effacement of the fold inconsistent. Support and filling work; traction mostly does not.
Why the fold resists being "lifted"
The seam is stitched to muscle, so pulling the cheek sideways or upward moves the cheek, not the fold: a 77-patient imaging study found cheek filler does not shift the fold’s skin, and a 16-study review found facelift effacement of the fold inconsistent. Support and filling work; traction mostly does not.
Because the lip side of the seam is anchored to muscle, treatments that pull on the cheek move the cheek and leave the seam where it was. Three-dimensional imaging of 77 patients after cheek filler found the skin expanding over the injection site with no lateral traction on the fold, and a visible improvement in the medial face only when the nose-to-cheek transition itself was filled (PRS, 2018). The surgical literature says the same at larger scale: a review of 16 cohort and comparative facelift studies found many techniques giving statistically significant, patient-satisfying improvement, but objective, durable effacement of the fold inconsistent — the SMAS layer that surgeons tighten thins out exactly where the fold sits (systematic review).
What works is replacing what was lost next to the seam — bone-level support beside the nose, medial cheek volume, and a soft gel under the crease itself — and, for genuine descent, repositioning the tissue rather than stretching it. The mistake this page exists to prevent is the opposite: syringe after syringe into the fold until it is flat, which produces a heavy, ape-like upper lip that reads as treatment, not youth.
Why it hasn't worked for you so far
Nasolabial folds: fixable or here to stay?
What's real: filler under the fold is the best-evidenced injection in aesthetics, with 51 randomised trials behind it, and support in the medial cheek and beside the nose reduces how much it needs. What's not: a fold lifted away, or one filled flat. Here's how to tell them apart:
-
The cream
It reaches the skin, not the fold
The fold deepens as the cheek above it descends and deflates and the bone beside the nose recedes (Mendelson & Wong). A retinoid and sunscreen soften the fine crease printed into thin skin; no trial of either has measured the fold itself.
-
The lift
Pulling the cheek leaves the seam
The lip side of the fold is anchored to muscle, so pulling the cheek moves the cheek. In three-dimensional imaging of 77 patients, filler on the cheek did not move the fold at all (PRS, 2018), and a review of 16 facelift studies found objective, durable effacement of the fold inconsistent (systematic review).
-
The one nobody mentions
Weight lost after 45
Facial fat leaves with body fat. People who lost more than 10% of their weight after 45 showed markedly deeper folds (ASPS), and in 20 people on GLP-1 drugs midface volume fell by a median 9%, about 7% for every 10 kg lost (2025 imaging study).
The science
Nasolabial folds — what the evidence says
Every option, strongest first. Open any row for the trials behind it.
At home: the skin and the habits
Moderate evidence Sunscreen and not smoking
The skin component only: daily sunscreen cut measured skin aging by 24% in the one randomised prevention trial, and the smoking twin has the deeper fold. Neither touches descent or bone.
Sunscreen and not smoking
The skin component only: daily sunscreen cut measured skin aging by 24% in the one randomised prevention trial, and the smoking twin has the deeper fold. Neither touches descent or bone.
The skin component only: daily sunscreen cut measured skin aging by 24% in the one randomised prevention trial, and the smoking twin has the deeper fold. Neither touches descent or bone.
Sun and smoke thin the dermis and rob it of recoil, which is the skin's share of a deep fold. Daily sunscreen users in the Nambour trial showed no detectable increase in skin aging over 4.5 years — 24% less than discretionary users (Hughes 2013) — and among identical twins discordant for smoking, the smoker had the worse nasolabial folds (twin study). Graded moderate rather than strong because no trial has measured the fold itself, and because the fold's main drivers — fat descent and bone — are not skin. The habit that prevents the crease from printing; not the habit that lifts a cheek.
- Best for
- everyone — the only prevention with any trial behind it
- Sessions
- Every morning
- Downtime
- None
- Cost
- €10–30 / month
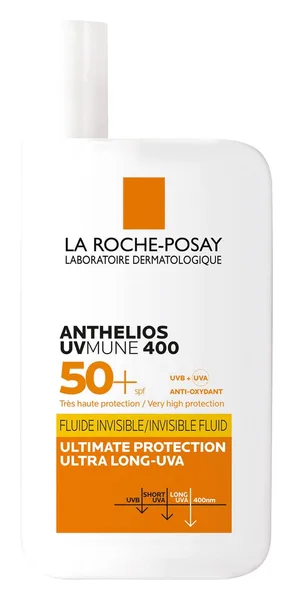
Our pick
La Roche-Posay Anthelios UVMune 400 Invisible Fluid SPF50+ — the unperfumed version: a water-resistant SPF 50+ fluid from a European pharmacy brand, with Mexoryl 400 for the longest UVA rays; 50 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
Emerging evidence A retinoid along the fold
Eight randomised tretinoin trials show fewer fine and coarse wrinkles; on the fold it softens the etched crease in thin skin and nothing else. Worth doing for the skin type; irrelevant to descent.
A retinoid along the fold
Eight randomised tretinoin trials show fewer fine and coarse wrinkles; on the fold it softens the etched crease in thin skin and nothing else. Worth doing for the skin type; irrelevant to descent.
Eight randomised tretinoin trials show fewer fine and coarse wrinkles; on the fold it softens the etched crease in thin skin and nothing else. Worth doing for the skin type; irrelevant to descent.
Tretinoin thickens the epidermis and rebuilds upper-dermal collagen; the meta-analysis of eight randomised trials in 1,361 patients found significant improvement in fine and coarse wrinkles over vehicle (meta-analysis). No trial has measured the nasolabial fold, and the mechanism can only reach the crease printed into thin skin — which is why the row sits at emerging for this problem despite strong evidence for wrinkles in general. For the skin type it is the base; for a heavy cheek it does nothing visible. The wrinkles guide covers the retinoid ladder.
- Sessions
- Nightly, indefinitely
- Downtime
- Weeks of dryness and peeling
- Cost
- €10–30 / month
Emerging evidence Weight stability rather than rapid loss
Facial fat goes with body fat: more than 10% weight loss after 45 deepens the folds, and after massive weight loss blinded raters judged faces about five years older, with the mid-cheek losing the most fat. Lose slowly, expect to replace volume, and avoid cycling.
Weight stability rather than rapid loss
Facial fat goes with body fat: more than 10% weight loss after 45 deepens the folds, and after massive weight loss blinded raters judged faces about five years older, with the mid-cheek losing the most fat. Lose slowly, expect to replace volume, and avoid cycling.
Facial fat goes with body fat: more than 10% weight loss after 45 deepens the folds, and after massive weight loss blinded raters judged faces about five years older, with the mid-cheek losing the most fat. Lose slowly, expect to replace volume, and avoid cycling.
Nobody should keep weight for a fold, but the trade should be known. Volumetric imaging shows deep and superficial facial fat both lost with weight loss, and deep fat is what props the cheek forward of the seam; people who lost more than 10% of body weight after 45 showed marked accentuation of the folds (ASPS), and a systematic review of massive weight loss found faces looking older — about five years older than their age to 40 blinded raters in one small study — with the most fat lost from the mid-cheek (systematic review). Slow loss gives the skin time to retract; weight cycling stretches it repeatedly; and the practical answer, for anyone on a weight-loss medication, is to budget for midface volume at the end of it rather than to stop.
- Sessions
- Ongoing
- Downtime
- None
- Cost
- Free
Emerging evidence Sleeping on your back
Side and stomach sleeping compress and shear the cheek against the pillow for hours; sleep wrinkles have their own distribution and worsen with age. Plausible, observational, free — and hard to enforce on a sleeping person.
Sleeping on your back
Side and stomach sleeping compress and shear the cheek against the pillow for hours; sleep wrinkles have their own distribution and worsen with age. Plausible, observational, free — and hard to enforce on a sleeping person.
Side and stomach sleeping compress and shear the cheek against the pillow for hours; sleep wrinkles have their own distribution and worsen with age. Plausible, observational, free — and hard to enforce on a sleeping person.
A cheek pressed into a pillow experiences compression, shear and tension for hours every night, and the review that named "sleep wrinkles" traces a set of lines — including those beside the nose and mouth — that follow that distortion rather than any expression, and worsen as skin loses elasticity (Anson 2016; 2012 study). No trial has randomised sleep position, most people cannot hold one asleep, and the fold's deep drivers are untouched; a contoured pillow and a silk pillowcase are cheap experiments, not treatments.
- Sessions
- Every night
- Downtime
- None
- Cost
- Free (€30–80 for a contoured pillow)
Limited evidence Facial exercise
The best-known facial-exercise pilot found fuller upper and lower cheeks after 20 weeks in 16 women, judged by blinded raters, with no control group; the one controlled study that graded the folds found no difference.
Facial exercise
The best-known facial-exercise pilot found fuller upper and lower cheeks after 20 weeks in 16 women, judged by blinded raters, with no control group; the one controlled study that graded the folds found no difference.
The best-known facial-exercise pilot found fuller upper and lower cheeks after 20 weeks in 16 women, judged by blinded raters, with no control group; the one controlled study that graded the folds found no difference.
This is the one concern where the facial-exercise evidence is relevant: the 20-week programme pilot in 16 middle-aged women found blinded dermatologists rating upper- and lower-cheek fullness improved and estimating faces about three years younger, the authors proposing muscle hypertrophy beneath the cheek (Alam 2018). It had no control group, measured no fold, and asked for half an hour a day; the same movements etch expression lines elsewhere. The one controlled study that graded the nasolabial folds — 18 people, seven weeks of daily exercises — found no difference there (only the upper lip was judged younger-looking), and its authors concluded "It cannot be concluded that facial exercises are effective" (De Vos 2013). Limited, then: the pilot's outcome is the tissue that props the fold, but the controlled data on the fold itself are negative.
- Sessions
- 30 minutes daily, then alternate days
- Downtime
- None
- Cost
- Free
Limited evidence Gua sha, rollers, microcurrent and "lifting" masks
Massage shifts facial contour by millimetres; one small industry-supported trial of a muscle-stimulation device reported shallower folds; nothing handheld repositions a fat pad or rebuilds bone. Pleasant, harmless, not treatment.
Gua sha, rollers, microcurrent and "lifting" masks
Massage shifts facial contour by millimetres; one small industry-supported trial of a muscle-stimulation device reported shallower folds; nothing handheld repositions a fat pad or rebuilds bone. Pleasant, harmless, not treatment.
Massage shifts facial contour by millimetres; one small industry-supported trial of a muscle-stimulation device reported shallower folds; nothing handheld repositions a fat pad or rebuilds bone. Pleasant, harmless, not treatment.
The consumer "lifting" shelf is drainage and sensation. Gua sha and rollers leave the cheek flushed — a roller raised cheek blood flow for at least ten minutes (Miyaji 2018) — and when 34 women were randomised to one or the other for eight weeks, facial contour distances were 2.2 to 3.3 mm shorter in both groups, with no untreated group and no fold among the measurements (Ahn 2025). Microcurrent and muscle-stimulation devices claim to tone the muscles under the cheek: a randomised trial in 108 women found the zygomatic major 18.6% thicker on blinded ultrasound after 12 weeks without measuring the fold (Kavanagh 2012), and the only controlled trial we found that measured the fold, an industry-supported split-face study of a high-frequency stimulation device in 24 women, reported a shallower maximum fold depth on the treated side after eight weeks (Omatsu 2024; 2026 correction). Sheet masks hydrate the crease for an evening. None reaches the malar fat pad, the deep cheek fat or the pyriform bone, which are the fold's drivers. Fine as ritual; not a line on this page's plan.
- Sessions
- As desired
- Downtime
- None
- Cost
- €15–400
Injectables
Strong evidence Hyaluronic-acid filler under the fold
The best-evidenced injection in aesthetics: 51 randomised trials, 4,097 people, wrinkle scores from 3.2 to 1.8 at a month and 2.5 at a year; the original 2003 trial found HA superior to collagen in 57–62% of patients. Reversible, about a year.
Hyaluronic-acid filler under the fold
The best-evidenced injection in aesthetics: 51 randomised trials, 4,097 people, wrinkle scores from 3.2 to 1.8 at a month and 2.5 at a year; the original 2003 trial found HA superior to collagen in 57–62% of patients. Reversible, about a year.
The best-evidenced injection in aesthetics: 51 randomised trials, 4,097 people, wrinkle scores from 3.2 to 1.8 at a month and 2.5 at a year; the original 2003 trial found HA superior to collagen in 57–62% of patients. Reversible, about a year.
Every modern filler earned its licence in the nasolabial fold, so the fold has the deepest randomised evidence in aesthetic medicine. The founding trial randomised 138 patients to hyaluronic acid or bovine collagen, one per side: at six months HA was judged superior in 56.9% of patients by wrinkle score and 62% by global improvement, against 9.5% and 8% for collagen, with less volume needed (Narins 2003). The meta-analysis of 51 randomised trials in 4,097 participants across 13 countries puts numbers on the class: mean wrinkle severity fell from 3.23 to 1.79 at one month, 2.02 at six and 2.46 at twelve, a "sustainable, up to one year" correction (meta-analysis). Newer gels are trialled against older ones for a year or more — a 64-week randomised within-subject study of a resilient HA (RHA trial), an 18-month open-label extension of a cohesive gel (Belotero extension), a registered 18-month controlled trial of a mid-viscosity gel (Volift trial) — and a 2024 network meta-analysis ranks them with little daylight between the major brands (network meta-analysis).
Placement decides the look: a medium gel in the deep dermis or just beneath it along the crease, threaded with a cannula from below, never enough to flatten the fold, and always after the support rows — a fold filled before the cheek is supported needs twice the gel and reads as a heavy lip. Hyaluronidase reverses it. The filler guide covers products, MRI persistence and the reversal drug.
- Best for
- the fold at rest, after support behind it — the reversible first step for almost everyone
- Sessions
- Every 9–15 months
- Downtime
- 2–5 days of swelling; bruising
- Cost
- €300–600 per syringe (UK £300–630)

Available at a partner clinic
EGP Aesthetics — Filler for nasolabial folds (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £290, 30 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Strong evidence Calcium hydroxylapatite (Radiesse) in the fold
Two randomised split-face trials: superior to collagen in 79% of folds at six months in the 117-patient pivotal study, and still improved in 79% of folds at 12 months against 43% for hyaluronic acid in the head-to-head. Longer-lasting, firmer, not reversible.
Calcium hydroxylapatite (Radiesse) in the fold
Two randomised split-face trials: superior to collagen in 79% of folds at six months in the 117-patient pivotal study, and still improved in 79% of folds at 12 months against 43% for hyaluronic acid in the head-to-head. Longer-lasting, firmer, not reversible.
Two randomised split-face trials: superior to collagen in 79% of folds at six months in the 117-patient pivotal study, and still improved in 79% of folds at 12 months against 43% for hyaluronic acid in the head-to-head. Longer-lasting, firmer, not reversible.
Calcium hydroxylapatite microspheres in a gel carrier fill immediately and then provoke collagen around each sphere as the carrier is absorbed. Its pivotal trial randomised 117 patients with symmetric folds to calcium hydroxylapatite on one side and human collagen on the other: at six months it was rated superior in 79% of folds with about half the volume (decade review), and the 12-month multicentre split-face trial against non-animal stabilised hyaluronic acid found it more effective at every time point, with 79% of folds still improved at a year against 43% and 30% less volume used (split-face RCT); long-term follow-up confirmed safety (long-term study). Biopsies show it drives more active collagen remodelling than hyaluronic acid (histology study).
The trade is reversibility: there is no enzyme for it, it is too firm for thin skin and for the lip, and a vascular occlusion with it is harder to treat. Deep placement under a thick-skinned fold, by someone who uses it weekly.
- Best for
- a deep fold in thicker skin, when you want 12–18 months and accept there is no eraser
- Sessions
- Every 12–18 months
- Downtime
- 3–7 days of swelling; bruising
- Cost
- €350–600 per syringe (UK from £345–410)
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Moderate evidence Medial cheek and nose-to-cheek support first
Restoring the deep medial cheek improves satisfaction with the untreated fold in the Voluma trial, but 3D imaging of 77 patients shows lateral cheek filler does not move the fold at all — the gain comes from the medial cheek and the nose-to-cheek transition, not from "lifting".
Medial cheek and nose-to-cheek support first
Restoring the deep medial cheek improves satisfaction with the untreated fold in the Voluma trial, but 3D imaging of 77 patients shows lateral cheek filler does not move the fold at all — the gain comes from the medial cheek and the nose-to-cheek transition, not from "lifting".
Restoring the deep medial cheek improves satisfaction with the untreated fold in the Voluma trial, but 3D imaging of 77 patients shows lateral cheek filler does not move the fold at all — the gain comes from the medial cheek and the nose-to-cheek transition, not from "lifting".
"Treat the cheek first" is the injector's mantra, and it is half right. In the pivotal Voluma programme, 235 patients had midface volume restored with a control group, and patient satisfaction improved in untreated regions including the nasolabial folds at six months and two years, plausibly because the medial cheek compartment was re-supported (pivotal RCT; two-year outcomes). But when 77 patients were imaged in three dimensions before and after cheek filler, 3 ml in the cheek produced expansion over the injection site and no traction on the skin between it and the fold — no photographic change in the fold at all — and only those filled at the nose-to-cheek transition showed the medial face improve (PRS, 2018).
So the evidence supports support, not lift: gel in the deep medial cheek fat and along the nasojugal transition props the tissue above the seam; gel on the lateral cheekbone makes a cheekbone and leaves the fold alone. Ask exactly where the syringe is going. The filler guide and the jowls guide grade the midface tools.
- Best for
- the heavy-cheek and hybrid types — the support that reduces what the fold needs, if it goes in the right place
- Sessions
- Every 12–24 months
- Downtime
- 3–7 days of swelling
- Cost
- €500–1,200 (2–4 ml)
Available at a partner clinic
EGP Aesthetics — Dermal Fillers - Cheeks (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £390, 45 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Poly-L-lactic acid (Sculptra and successors)
A randomised trial of 233 patients found PLLA more effective than collagen from month 3 to 13 with correction lasting up to 25 months in the open extension; a 252-person double-blind trial of PLLA microspheres found 92% of folds still corrected at 48 weeks against 59% with hyaluronic acid. Gradual, long, not reversible, nodules possible.
Poly-L-lactic acid (Sculptra and successors)
A randomised trial of 233 patients found PLLA more effective than collagen from month 3 to 13 with correction lasting up to 25 months in the open extension; a 252-person double-blind trial of PLLA microspheres found 92% of folds still corrected at 48 weeks against 59% with hyaluronic acid. Gradual, long, not reversible, nodules possible.
A randomised trial of 233 patients found PLLA more effective than collagen from month 3 to 13 with correction lasting up to 25 months in the open extension; a 252-person double-blind trial of PLLA microspheres found 92% of folds still corrected at 48 weeks against 59% with hyaluronic acid. Gradual, long, not reversible, nodules possible.
Poly-L-lactic acid is a collagen stimulator rather than a filler: injected as a suspension, it provokes fibroblasts over months and the volume arrives slowly. The pivotal randomised, evaluator-blinded trial gave 116 patients PLLA and 117 human collagen for nasolabial folds: PLLA scored significantly higher from month 3 through 13, and correction in the PLLA arm persisted to 25 months (Narins 2010, JAAD; investigator ratings). A newer microsphere formulation was tested in a 252-person multicentre double-blind randomised trial against hyaluronic acid: 92.4% of folds still corrected at 48 weeks against 59.3% (2026 RCT), and a split-face non-inferiority trial compares brands (split-face RCT). Graded moderate rather than strong because the 25-month figure comes from an uncontrolled extension, the effect is slow and operator-dependent, and there is no reversal. The regenerative guide covers the biostimulators.
- Sessions
- 2–3 sessions a month apart; repeat every 2 years
- Downtime
- 2–3 days; five days of massage
- Cost
- €500–800 per vial (UK from £525), usually 2–3 vials
Available at a partner clinic
EGP Aesthetics — Sculptra Collagen Biostimulator (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £950, 90 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Permanent PMMA–collagen filler (Bellafill)
The only permanent filler with long prospective data: 1,008 patients followed for five years after fold correction (871 completed), 83% satisfied, treatment-related events in 11.7% and biopsy-proven granulomas in 1.7%. Permanent means the mistakes are too.
Permanent PMMA–collagen filler (Bellafill)
The only permanent filler with long prospective data: 1,008 patients followed for five years after fold correction (871 completed), 83% satisfied, treatment-related events in 11.7% and biopsy-proven granulomas in 1.7%. Permanent means the mistakes are too.
The only permanent filler with long prospective data: 1,008 patients followed for five years after fold correction (871 completed), 83% satisfied, treatment-related events in 11.7% and biopsy-proven granulomas in 1.7%. Permanent means the mistakes are too.
Polymethylmethacrylate microspheres in bovine collagen stay for life, and the fold is where its safety was measured: a 23-site open-label study followed 1,008 patients for five years after nasolabial-fold correction, with 871 completing; 83% were satisfied or very satisfied, treatment-related adverse events occurred in 11.7% (mostly lumps and redness, mostly in the first year), and biopsy-confirmed granulomas in 1.7%, almost all responding to treatment (five-year study; 2026 review). Unavailable in much of Europe, requiring a skin test for the bovine collagen, and permanent in a face that will keep changing around it — a granuloma at year eight is surgery, not an enzyme. Moderate for the data's length; a last choice for most faces.
- Sessions
- Once, with a touch-up
- Downtime
- 3–7 days
- Cost
- €800–1,500 per syringe
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Moderate evidence Autologous fat grafting
A 62-patient randomised comparison found fat and hyaluronic acid equally effective for the folds over nine months, with fat ahead at twelve; your own tissue, an operation to harvest it, and only part of the graft survives, so a second session is common.
Autologous fat grafting
A 62-patient randomised comparison found fat and hyaluronic acid equally effective for the folds over nine months, with fat ahead at twelve; your own tissue, an operation to harvest it, and only part of the graft survives, so a second session is common.
A 62-patient randomised comparison found fat and hyaluronic acid equally effective for the folds over nine months, with fat ahead at twelve; your own tissue, an operation to harvest it, and only part of the graft survives, so a second session is common.
Fat harvested from the abdomen or thigh and placed in the medial cheek and along the fold replaces the deep fat that deflated, with tissue that behaves like the tissue around it. The one randomised comparison enrolled 62 patients (57 completing) to fat or hyaluronic acid in both folds: blinded wrinkle scores showed no difference within nine months and a significant advantage for fat at twelve, with early side effects differing and later ones similar (Hu 2017). The trade is that it is an operation with a donor site, that a variable fraction of the graft survives so a second session is common, that it cannot be dissolved, and that it follows body weight afterwards. Best combined with a facelift or done for a whole midface rather than a fold alone.
- Sessions
- Once, sometimes twice
- Downtime
- 1–2 weeks of swelling; donor-site bruising
- Cost
- €2,500–5,000
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Moderate evidence Polycaprolactone (Ellansé) and other collagen stimulators
A randomised trial found 88.8% of folds still improved at twelve months against 23.8% with a hyaluronic gel, and a 2025 comparison found it ahead of PLLA; longer-lasting than hyaluronic acid, no reversal, one trial.
Polycaprolactone (Ellansé) and other collagen stimulators
A randomised trial found 88.8% of folds still improved at twelve months against 23.8% with a hyaluronic gel, and a 2025 comparison found it ahead of PLLA; longer-lasting than hyaluronic acid, no reversal, one trial.
A randomised trial found 88.8% of folds still improved at twelve months against 23.8% with a hyaluronic gel, and a 2025 comparison found it ahead of PLLA; longer-lasting than hyaluronic acid, no reversal, one trial.
Polycaprolactone microspheres in a carrier gel fill immediately and stimulate collagen as they degrade over one to four years depending on the version. The fold is where it was tested: in a multicentre randomised trial of 160 patients, 88.8% of folds treated with polycaprolactone were still improved at twelve months against 23.8% with a hyaluronic gel, whose effect faded from the third month (randomised trial); a 2025 retrospective comparison of 136 patients found it ahead of poly-L-lactic acid at three, six and twelve months with similar safety (comparative study); and it is among the products pooled in the 51-trial meta-analysis (meta-analysis). One randomised trial, in Chinese patients, keeps it at moderate. Longer than hyaluronic acid, not reversible, and with the same nodule caveats as the other stimulators; the regenerative guide grades the class.
- Sessions
- Every 18–24 months
- Downtime
- 3–7 days
- Cost
- €400–700 per syringe
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Deep pyriform-space support at the base of the nose
A bolus of firm gel on the bone beside the nostril restores the shelf the fold hangs from; retrospective series and cadaver work support it, and migration from the space is a known failure. The right move for the bone type; not yet trialled.
Deep pyriform-space support at the base of the nose
A bolus of firm gel on the bone beside the nostril restores the shelf the fold hangs from; retrospective series and cadaver work support it, and migration from the space is a known failure. The right move for the bone type; not yet trialled.
A bolus of firm gel on the bone beside the nostril restores the shelf the fold hangs from; retrospective series and cadaver work support it, and migration from the space is a known failure. The right move for the bone type; not yet trialled.
Where the maxilla has receded, the fat-lined deep pyriform space beside the nostril enlarges, and injectors place a small bolus of high-G′ gel on the bone there to rebuild the shelf and lift the top of the fold. The evidence is technique-level: a retrospective clinical series of deep pyriform-space augmentation with a firm hyaluronic gel (retrospective study), cadaveric work mapping an adjacent "perialar space" for more stable placement because gel migrates out of the pyriform space (cadaveric study), and a combined-treatment proposal for the empty space (2025 proposal). The angular branch of the facial artery runs through this territory, which makes it a cannula-and-aspiration site for experienced hands only.
- Sessions
- Every 12–24 months
- Downtime
- 2–5 days
- Cost
- €300–600 (0.5–1 ml)
Available at a partner clinic
EGP Aesthetics — Filler for nasolabial folds (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £290, 30 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Emerging evidence Cultured autologous fibroblast injections
A pilot comparing injections of the patient’s own cultured fibroblasts with hyaluronic filler for the folds: slower, cell-based, and not something to buy yet.
Cultured autologous fibroblast injections
A pilot comparing injections of the patient’s own cultured fibroblasts with hyaluronic filler for the folds: slower, cell-based, and not something to buy yet.
A pilot comparing injections of the patient’s own cultured fibroblasts with hyaluronic filler for the folds: slower, cell-based, and not something to buy yet.
Fibroblasts grown from a punch biopsy of the patient's own skin and injected back along the fold aim to rebuild dermis rather than fill it. A pilot study compared cultured autologous fibroblast injections with hyaluronic acid filler for nasolabial folds and reported improvement that arrived more slowly than filler (pilot study). Biologically interesting, expensive, weeks of cell culture per treatment, and limited to a handful of research settings; the regenerative guide covers where cell therapies stand.
- Sessions
- 3 sessions; weeks of culture first
- Downtime
- 1–2 days
- Cost
- Not routinely available
Limited evidence Botulinum toxin for the fold
Toxin does not treat a nasolabial fold; the exception is the gummy smile, where a few units in the lip elevators beside the nose lower the lip and soften the medial fold for three to six months. Used as an adjunct to threads in one 32-patient study.
Botulinum toxin for the fold
Toxin does not treat a nasolabial fold; the exception is the gummy smile, where a few units in the lip elevators beside the nose lower the lip and soften the medial fold for three to six months. Used as an adjunct to threads in one 32-patient study.
Toxin does not treat a nasolabial fold; the exception is the gummy smile, where a few units in the lip elevators beside the nose lower the lip and soften the medial fold for three to six months. Used as an adjunct to threads in one 32-patient study.
Weakening the lip elevators to soften a fold flattens the smile, so toxin is not a nasolabial-fold treatment. The one legitimate use is the gummy smile: a small dose into the levator labii superioris alaeque nasi beside each nostril lowers the lip for 12–24 weeks with high satisfaction, and the deep medial folds these patients carry soften with it (narrative review; systematic review of dose and site). A prospective comparison of 32 patients found toxin given an hour after thread lifting prolonged the threads' effect on the fold to six months (comparative study) — an adjunct, not a treatment. Limited for the fold itself.
- Sessions
- Every 3–6 months (gummy smile only)
- Downtime
- None
- Cost
- €100–200
Lifting, releasing and surgery
Moderate evidence Facelift (SMAS, extended SMAS, deep plane)
For true descent, the only treatment that repositions the cheek — yet a review of 16 studies found objective, durable effacement of the fold inconsistent, because the tissue layer surgeons tighten thins out where the fold sits. Satisfaction high, fold correction modest.
Facelift (SMAS, extended SMAS, deep plane)
For true descent, the only treatment that repositions the cheek — yet a review of 16 studies found objective, durable effacement of the fold inconsistent, because the tissue layer surgeons tighten thins out where the fold sits. Satisfaction high, fold correction modest.
For true descent, the only treatment that repositions the cheek — yet a review of 16 studies found objective, durable effacement of the fold inconsistent, because the tissue layer surgeons tighten thins out where the fold sits. Satisfaction high, fold correction modest.
A facelift repositions the descended cheek and tightens the SMAS layer beneath the skin, and for the heavy-cheek type it is the one treatment that moves tissue rather than adding it. The honest summary comes from the surgical literature itself: a critical review of 16 cohort and comparative studies from 2000 to 2025 — skin-only, SMAS plication, limited SMASectomy, extended SMAS and deep-plane composite lifts — found many techniques giving statistically significant, patient-satisfying improvement, but objective long-term effacement of the fold inconsistent and "lacking" data to favour any technique, because the SMAS layer is absent or attenuated beneath the fold's own fat, so extended and deep-plane dissection has limited purchase there (systematic review). Meta-analysis finds deep-plane and SMAS lifts comparable overall (meta-analysis), and some surgeons graft SMAS into the fold at the same operation (SMAS graft).
Have the facelift for the jowls and neck, and expect the fold to soften; do not have it for the fold. Fat grafting to the medial cheek at the same operation is how surgeons close the gap. The jowls guide and the 50s guide grade the surgery.
- Best for
- a heavy cheek with jowls and neck — the fold improves as a by-product, never as the reason for the operation
- Sessions
- Once; 10–15 years
- Downtime
- 2–3 weeks; final at 6–12 months
- Cost
- €8,000–20,000 (UK £8,000–15,000; mid-facelift £5,000–8,000)
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Thread lifts (PDO cog threads)
A 32-patient comparison found threads shallowed the fold from about 2.3 to 1.8 mm at six months with partial recurrence, and a systematic review calls the technique scarcely studied; months, not years, with dimpling and extrusion.
Thread lifts (PDO cog threads)
A 32-patient comparison found threads shallowed the fold from about 2.3 to 1.8 mm at six months with partial recurrence, and a systematic review calls the technique scarcely studied; months, not years, with dimpling and extrusion.
A 32-patient comparison found threads shallowed the fold from about 2.3 to 1.8 mm at six months with partial recurrence, and a systematic review calls the technique scarcely studied; months, not years, with dimpling and extrusion.
Barbed absorbable threads passed under the cheek and anchored above catch tissue and hitch it upward, then dissolve over months leaving a little collagen. The fold data are small: in a prospective comparison of 32 patients aged 40–65, threads alone brought fold depth to 1.8 ± 0.3 mm at six months with partial recurrence, and threads plus toxin to 1.5 ± 0.3 mm (comparative study); technique papers describe reverse-vector threads aimed at the fold specifically (technique paper); and the systematic review of PDO threads calls them a scarcely studied technique (systematic review). The lift is measured in months, the fold recurs first, and dimpling, thread visibility and extrusion are the routine complications. The jowls guide grades threads for the lower face.
- Sessions
- Every 12–18 months
- Downtime
- 3–7 days; dimpling for weeks
- Cost
- €800–2,000 (mid-face)
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Subcision of the fold
A needle swept under the crease to release its tethering: in 16 women, the mean improvement fell from 43% at a month to 19% at six months, with bruising in a third. Cheap, real for the tethered crease, temporary alone.
Subcision of the fold
A needle swept under the crease to release its tethering: in 16 women, the mean improvement fell from 43% at a month to 19% at six months, with bruising in a third. Cheap, real for the tethered crease, temporary alone.
A needle swept under the crease to release its tethering: in 16 women, the mean improvement fell from 43% at a month to 19% at six months, with bruising in a third. Cheap, real for the tethered crease, temporary alone.
Because the lip side of the fold is stitched to muscle by short septa, releasing those septa with a needle lets the crease float free — subcision, borrowed from acne-scar work. An open-label study treated 16 women aged 33–60 with an 18-gauge needle fanned at the dermal–fat junction under local anaesthetic: 81% showed moderate improvement at one month (mean 42.8%), falling to a mean 18.8% improvement at six months, with skin elasticity measurably increased and mild bruising in 31% (open-label study). No control group and a fading effect, but the mechanism is right for the tethered crease, and combining it with filler placed into the released space is how injectors use it.
- Sessions
- 1–2
- Downtime
- 2–3 days of bruising
- Cost
- €200–500
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Monopolar radiofrequency (Thermage and successors)
In a 20-patient randomised comparison, two Thermage treatments improved the folds significantly at four months where one did not; newer devices show measurable fold-area reductions over six months. Softening for mild laxity, not repositioning.
Monopolar radiofrequency (Thermage and successors)
In a 20-patient randomised comparison, two Thermage treatments improved the folds significantly at four months where one did not; newer devices show measurable fold-area reductions over six months. Softening for mild laxity, not repositioning.
In a 20-patient randomised comparison, two Thermage treatments improved the folds significantly at four months where one did not; newer devices show measurable fold-area reductions over six months. Softening for mild laxity, not repositioning.
Monopolar radiofrequency heats the deep dermis and the fibrous septa to contract them, and the nasolabial fold was the endpoint in its first randomised study: 20 patients with mild to moderate laxity received one or two treatments, and the two-treatment group improved significantly more at the folds at four months, though both groups improved, with 75% willing to pay for more despite modest change (2004 study). Newer monopolar devices report measurable nasolabial-fold improvement on 3D imaging in pilot and randomised work (2025 pilot; 2025 RCT), and a bimodal system a reduction in fold cross-sectional area over six months (2026 study). It tightens skin over a fold; it does not move the fat pad or rebuild bone. Fine for the skin type with mild laxity; the jowls guide grades the devices.
- Sessions
- 1–2, repeated yearly
- Downtime
- None to a day
- Cost
- €1,000–2,500
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Microfocused ultrasound (Ultherapy and successors)
A randomised split-face trial of an intelligent microfocused ultrasound shortened the fold by 18.5% at two months; the class lifts by millimetres in meta-analysis. Modest, safe in good hands, and temporary.
Microfocused ultrasound (Ultherapy and successors)
A randomised split-face trial of an intelligent microfocused ultrasound shortened the fold by 18.5% at two months; the class lifts by millimetres in meta-analysis. Modest, safe in good hands, and temporary.
A randomised split-face trial of an intelligent microfocused ultrasound shortened the fold by 18.5% at two months; the class lifts by millimetres in meta-analysis. Modest, safe in good hands, and temporary.
Focused ultrasound heats points in the SMAS and deep dermis to contract them, and the fold is one of its measured endpoints: in a multicentre randomised split-face study, the treated side's nasolabial-fold length fell by 18.5% at two months (split-face RCT); a split-face trial combining it with microneedle radiofrequency improved wrinkle-severity scores (combination trial); and the systematic review of the class finds consistent but modest tightening (systematic review; meta-analysis). A fifth shorter is real and is not a repositioned cheek; it suits mild descent in someone who will not have surgery, and it can melt fat in a cheek that has none to spare. The jowls guide grades HIFU in detail.
- Sessions
- Once a year
- Downtime
- None; days of tenderness
- Cost
- €1,000–3,000
Available at a partner clinic
EGP Aesthetics — Ultrasound Lift & Tighten Face/Body (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £190, 60 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Emerging evidence Direct excision of the fold
Cutting the fold out and closing it in the crease: durable in a series of more than 30 patients and a smaller one of 9, scars unnoticeable within six months in the reports — for older men with sun-damaged skin and deep folds, almost never for anyone else.
Direct excision of the fold
Cutting the fold out and closing it in the crease: durable in a series of more than 30 patients and a smaller one of 9, scars unnoticeable within six months in the reports — for older men with sun-damaged skin and deep folds, almost never for anyone else.
Cutting the fold out and closing it in the crease: durable in a series of more than 30 patients and a smaller one of 9, scars unnoticeable within six months in the reports — for older men with sun-damaged skin and deep folds, almost never for anyone else.
The bluntest instrument: an ellipse of skin excised along the fold and closed so the scar lies in the crease. The plastic-surgery series report it as effective and durable in selected patients — chiefly men with thick, sun-damaged skin and very deep folds, in whom a scar hides — with scars unnoticeable within six months and results holding at eighteen (PRS, 1999; 2005 series). For a woman with fine skin the scar is the new problem, which is why the technique lives at the edge of practice and in facial-palsy and lipoatrophy work rather than routine aesthetics.
- Sessions
- Once
- Downtime
- 1–2 weeks; scar matures over months
- Cost
- €1,500–3,000
Emerging evidence Restoring the support underneath (teeth, dentures, the maxilla)
Loss of upper teeth resorbs the bone the fold hangs from and deepens it; prosthodontists check denture flange thickness for exactly this. Emerging because nobody has randomised a denture against a syringe.
Restoring the support underneath (teeth, dentures, the maxilla)
Loss of upper teeth resorbs the bone the fold hangs from and deepens it; prosthodontists check denture flange thickness for exactly this. Emerging because nobody has randomised a denture against a syringe.
Loss of upper teeth resorbs the bone the fold hangs from and deepens it; prosthodontists check denture flange thickness for exactly this. Emerging because nobody has randomised a denture against a syringe.
The top of the fold rests on the maxilla and the teeth in it. Losing upper teeth starts irreversible resorption of the alveolar ridge — about half its width in the first year — and the visible result is a collapsed upper lip and deep nasolabial folds, which is why prosthodontists inspect the thickness of a denture's flange as lip and cheek support (prosthodontic review; bone loss and teeth). For anyone with worn dentures, missing upper teeth or a collapsed bite, the dentist's assessment comes before the injector's, and filler on the pyriform bone is the bridge between them.
- Sessions
- Dental assessment
- Downtime
- By procedure
- Cost
- Varies widely
Limited evidence Fractional and ablative resurfacing over the fold
Resurfacing rebuilds skin and softens the etched crease in the skin type; it does not lift a fat pad or fill a groove. Only small or comparative studies have graded the fold itself, and the grade reflects those; on skin, the lasers work.
Fractional and ablative resurfacing over the fold
Resurfacing rebuilds skin and softens the etched crease in the skin type; it does not lift a fat pad or fill a groove. Only small or comparative studies have graded the fold itself, and the grade reflects those; on skin, the lasers work.
Resurfacing rebuilds skin and softens the etched crease in the skin type; it does not lift a fat pad or fill a groove. Only small or comparative studies have graded the fold itself, and the grade reflects those; on skin, the lasers work.
Fractional and full-field lasers remodel the dermis (Orringer 2004) and are the right tool for a fine line printed into thin skin along the fold — three fractional CO₂ sessions reduced wrinkles in all four facial areas measured, the cheeks most (Kohl 2014); they have no purchase on the fat, bone and descent that make the fold itself, and the few studies that graded the fold are small or comparative: in a 10-person split-face study of a fractional picosecond laser, 60% had shallower folds on the treated side (Ge 2016), and in 71 women, 16 weeks of a retinoid–peptide serum improved the folds more than a single fractional CO₂ session (Kruger 2025). Graded limited for this problem on that basis, not because the lasers do not work on skin — the wrinkles guide and the laser guide grade them for what they do.
- Sessions
- 1–3
- Downtime
- 5–14 days by depth
- Cost
- €400–2,000
The starting routine
What you can do at home
Skincare reaches one share of a fold: the crease printed into thin skin. The cheek, the bone and the deep fat are the next step. At home, two products and one habit:
-
Morning
Sunscreen every morning, and no smoking
Daily use meant 24% less measured skin aging over 4.5 years (Hughes 2013), and among identical twins the smoker had the worse folds. It keeps the crease from printing; it does not lift a cheek. The evidence.
Our pick
La Roche-Posay Anthelios UVMune 400 Invisible Fluid SPF50+ — the unperfumed version: a water-resistant SPF 50+ fluid from a European pharmacy brand, with Mexoryl 400 for the longest UVA rays; 50 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
-
Night, building up from two nights a week
A retinoid along the fold
Eight randomised tretinoin trials show fewer fine and coarse wrinkles; on the fold it softens the etched crease in thin skin and nothing else. Tretinoin on prescription is the strongest; without one, retinal. The evidence.
-
From now on
Keep your weight steady, and lose it slowly
Losing more than a tenth of your weight after 45 deepens the folds, and regaining it does not restore them neatly. Lose slowly, and budget for volume at the end rather than stopping. Sleeping on your back is a free experiment, not a treatment. The evidence.
None of this lifts a cheek or rebuilds bone: a fold that stays when you lie flat is the next step, below, support first and then a little under the fold, never filled flat. Not in pregnancy: the retinoids guide explains why.
The next step, proven clinical treatments
Where to have them done
Clinics that offer the treatments graded above, listed in the order of the evidence, with the clinic's own prices. A consultation first is the right first step for every treatment on this page.
Commercial note: listed clinics are partners and may pay us a referral fee when you book through our links. That has no bearing on how the evidence is graded, and clinics are ordered by the evidence, never by what they pay.
In your country
Elsewhere in Europe
Further afield
London, United Kingdom · nurse-led
EGP Aesthetics
Nurse-led aesthetic clinic in London SW8, offering advanced non-surgical and biostimulating treatments (Profhilo, polynucleotides, PRP, exosomes and Sculptra) for natural-looking results.
809 Wandsworth Road, SW8 3JH · English spoken
Interactive
Match a plan to your folds
Which fold do you have? Open the one that looks like yours: first how to tell, then the plan, each link jumping to the graded section in the order to try them.
The fold softens or vanishes when I lie on my back
How to tell
Lie flat with a hand mirror. If the fold softens or disappears as the cheek falls back, with a soft roll of cheek above it when you sit up, the problem is above the seam: the cheek fat has slid down and the deep cheek fat has emptied. The commonest type after fifty, and the one where filling the fold itself satisfies least.
The plan
01 The heavy cheek descent and deflation above an anchored seam 02 Medial cheek and nose-to-cheek support props the tissue above the fold — if it goes in the right place 03 Then a little under the fold the 51-trial evidence, with less gel 04 Surgery, if there are jowls and a neck too the only treatment that repositions — with the fold as a bonus A deep groove beside my nose that stays when I lie down
How to tell
Run a fingertip from the nostril down the fold. If the deepest point is at the top, in a hollow beside the wing of the nose that does not change when you lie down, the deficit is bone: the upper jaw and the rim beside the nose have receded, and filler in the fold alone leaves the hollow.
The plan
01 Bone retrusion the maxilla and pyriform rim have receded 02 Deep pyriform-space support rebuilds the shelf the fold hangs from 03 Then the fold medium gel under the crease, never flat 04 Check the teeth lost upper teeth resorb the bone underneath A fine crease in thin, sun-damaged skin, without much of a roll above it
How to tell
Pinch the skin at the fold. If it is thin, settles back slowly and carries a fine etched line rather than a deep fold, with little roll above it, the skin itself is the problem: sun and smoking have thinned it, and deep volume would show as a ridge.
The plan
01 The fine crease the skin has lost recoil — deep volume is wasted here 02 A retinoid and sunscreen the wrinkle toolkit, for the skin type only 03 A soft gel threaded along the crease superficial and sparing, with a cannula 04 Subcision for a tethered crease releases the septa the seam is stitched with It only shows when I smile — and my gums show too
How to tell
Smile, then relax. A fold that appears only when you smile and is gone at rest is the seam doing its job, at any age: nothing to treat, and filler placed to hide it shows as a ridge across the smile. Only when the gums show too does a little toxin beside the nose help.
The plan
01 The fold that only appears on smiling normal anatomy — do not fill it 02 Toxin for the gummy smile only a few units beside the nose lower the lip and soften the medial fold I lost a lot of weight and the folds deepened
How to tell
The folds deepened as you lost weight, above all more than a tenth of your weight after 45 or on a GLP-1 medicine: the fat that propped the cheek forward went with the rest. In the imaging study midface volume fell by a median 9%, about 7% for every 10 kg lost, and regaining weight does not refill it neatly.
The plan
01 What weight loss did facial fat leaves with body fat 02 Keep the weight off, replace the volume the trade, stated plainly 03 Medial cheek support put the volume back where it came from 04 Fat grafting for large losses your own tissue, matched hyaluronic acid in the one randomised comparison I want the longest-lasting option
How to tell
You have had hyaluronic acid, know how your fold behaves under it, and want each round to last longer than a year. Nothing that lasts longer can be dissolved: start with what dissolves, and move on only once you know your fold.
The plan
01 What actually lasts and what it costs to have it not dissolve 02 Calcium hydroxylapatite 79% of folds still improved at a year against 43% for HA 03 Poly-L-lactic acid to 25 months in the pivotal extension 04 PMMA, with eyes open five-year data on 1,008 patients, 1.7% granulomas, permanent I am nervous about filler near my nose
How to tell
The artery is what worries you: the facial artery runs under the fold, which makes it the commonest site of filler-induced skin necrosis. In a large practitioner survey, occlusion came at about 1 in 6,410 syringes by needle and 1 in 40,882 by cannula, and 84% of hyaluronic-acid occlusions recover at least partly with prompt hyaluronidase.
The plan
01 The artery under the fold the numbers, and what makes it safer 02 Hyaluronic acid by cannula reversible, and six times fewer occlusions than a needle 03 Or a device, for mild laxity no artery risk, a fifth of the effectIn more detail
The heavy cheek (descent and deflation)
The heavy cheek (descent and deflation)
Lie flat and look in a hand mirror. If the fold softens or disappears as the cheek falls back, the problem is above the seam: the malar fat pad has migrated down and the deep medial cheek fat that once held it forward has deflated, so tissue heaps against the anchored fold. This is the commonest type after fifty, and the one where filling the fold itself is least satisfying — the roll above simply overhangs a flatter crease. The order is support (deep medial cheek and the nose-to-cheek transition), a little in the fold, and, for real descent, a repositioning operation; threads and devices promise the lift and deliver a fraction of it.
The deep groove beside the nose (bone retrusion)
The deep groove beside the nose (bone retrusion)
Run a finger from the nostril down the fold. If the deepest point is at the top, in a hollow beside the wing of the nose that does not change lying down, the deficit is skeletal: the maxilla and the edge of the pyriform aperture resorb with age, and the fat-lined "deep pyriform space" beside the nostril enlarges as bone and fat retreat together (piriform fossa). Filler into the fold alone leaves the hollow; a deep bolus on the bone at the pyriform aperture restores the shelf the fold hangs from, and is where an experienced injector starts. A bony deficit is also the one type that a facelift cannot touch.
The fine crease in thin skin
The fine crease in thin skin
Pinch the skin at the fold. If it is thin, tents slowly and carries a fine etched line rather than a deep fold, the skin itself is the problem: sun and smoking have thinned the dermis and the crease has printed into it. This type wants the wrinkle toolkit — a retinoid, sunscreen, a soft low-viscosity gel threaded superficially along the crease, and fractional resurfacing for the etched line — and it responds badly to deep volume, which sits under thin skin as a visible ridge. Our wrinkles guide grades the skin tools in detail.
The fold that only appears when you smile
The fold that only appears when you smile
A fold that appears on smiling and disappears at rest is the seam doing its job, and no treatment is indicated; filler placed to hide it shows as a ridge across a smile. The exception is the "gummy smile": when the levator labii superioris alaeque nasi pulls the lip so high that gum shows, a small dose of botulinum toxin beside the nose lowers the lip for three to six months, and these patients' unusually deep medial folds soften with it (narrative review). For everyone else, toxin does not treat the nasolabial fold.
Weight, sleep position and the fold
Weight, sleep position and the fold
Two habits move the fold and are rarely mentioned. Facial fat is lost with body weight: people who lost more than 10% of their weight after 45 showed marked deepening of the folds (ASPS), and in a CT and MRI study of 20 people on GLP-1 drugs, midface volume fell by a median 9% — about 7% for every 10 kg lost — most of it from the superficial fat (2025 imaging study). Sleep is the other: compression, shear and tension on a cheek pressed into a pillow for hours every night produce "sleep wrinkles" whose distribution differs from expression lines, and the nasolabial region takes the load in side-sleepers (Anson 2016; 2012 study). Neither is something to fix a fold with; both are worth knowing before you spend.
The recline test, the smile test and the finger
The recline test, the smile test and the finger
Three tests sort a fold in a minute. Lie flat with a hand mirror: a fold that softens as the cheek falls back is descent and deflation; one that stays is a volume or bony deficit. Smile and relax: a fold present only on smiling is anatomy, not a problem. Run a fingertip from nostril to mouth corner: a groove deepest at the top, in a hollow beside the nose, is bone retrusion and wants deep support; a fold deepest in its middle is fat and skin. Pinch the skin for thinness. Then photograph from slightly below in one light, at rest and smiling — the fold changes with hydration, salt, sleep and the angle of the camera, and every treatment on this page is judged against that picture.
The action plan
The plan, month by month
What happens in which order — and when it is fair to judge it. The skin first, the support second, the fold third, the knife last and only for the right reasons.
Week 0: recline, smile, run a finger — and photograph
Descent, bone or skin; smiling-only is normal; teeth and dentures checked; a photograph from below in one light.
Day 1 onward: the skin base and the two habits
Sunscreen, no smoking, a retinoid along the fold; back-sleeping if you can; lose weight slowly and budget for volume after.
Month 1: support first, then the fold
Deep medial cheek and, for the bone type, the pyriform aperture — then a medium gel under the crease by cannula, stopping while the fold is still there.
Months 12–24: trade up, or reposition
Calcium hydroxylapatite or PLLA for one to two years a round; a facelift with fat grafting only if jowls and neck justify it.
Frequently asked questions
Aren't smile lines normal? Should I treat them at all?
Smiling yes; at rest, your call
Aren't smile lines normal? Should I treat them at all?
Smiling yes; at rest, your call
A nasolabial fold is a seam between two kinds of tissue and appears in every smile from childhood; filling the crease you see when you smile produces a ridge across the smile. What ages is the fold at rest — deeper each decade as the cheek descends, the bone recedes and the skin thins — and the only reason to treat it is that the resting fold bothers you. Treated well, a fold is supported and softened and still visible; a face without one looks filled, not young.
Fill the fold, or fill the cheek?
Support first, then fold
Fill the fold, or fill the cheek?
Support first, then fold
Both, in the right order and the right places. The fold's evidence is the deepest in aesthetics — 51 randomised trials — but a fold filled before the tissue above and beside it is supported needs twice the gel and reads as a heavy upper lip. Support means the deep medial cheek fat, the nose-to-cheek transition and, for the bone type, a bolus on the pyriform aperture; it does not mean the lateral cheekbone, which 3D imaging of 77 patients showed expands over the injection and leaves the fold's skin exactly where it was. Then a soft to medium gel threaded under the crease itself, stopping while the fold is still there.
How long does filler last in the fold?
About a year (HA)
How long does filler last in the fold?
About a year (HA)
The meta-analysis of 51 trials gives the shape of the curve for hyaluronic acid: mean wrinkle severity from 3.23 to 1.79 at one month, 2.02 at six, 2.46 at twelve — most of the gain still there at a year. Calcium hydroxylapatite held 79% of folds improved at twelve months against 43% for hyaluronic acid in the head-to-head; poly-L-lactic acid lasted to 25 months in its extension; fat matched hyaluronic acid for nine months and led at twelve; PMMA is permanent. MRI finds hyaluronic gel persisting for years after it has stopped being visible, which argues for top-ups on the photograph, not the calendar.
Will a facelift get rid of them?
Softens, rarely erases
Will a facelift get rid of them?
Softens, rarely erases
A facelift repositions the descended cheek, and for the heavy-cheek type the fold softens with it; a bony groove beside the nose does not change. The review of 16 studies found high satisfaction with modest fold correction and no technique with objective long-term data behind it, because the SMAS layer that extended and deep-plane lifts pull on is absent or thin beneath the fold's fat. Surgeons close the gap with fat grafting to the medial cheek during the operation, and the fold is treated afterwards with a little filler if it needs it. Nobody should have a facelift for a fold; plenty of people with jowls and a neck get a better fold as a bonus.
Are threads worth it for the folds?
Rarely
Are threads worth it for the folds?
Rarely
Threads hitch tissue upward and dissolve; the evidence for the fold is one prospective comparison of 32 patients in which threads alone shallowed the fold to 1.8 mm at six months with partial recurrence, and the systematic review of the technique calls it scarcely studied with under-reported complications. For someone with mild descent who will not have surgery and understands that the result is measured in months, a mid-face thread lift is a legitimate choice; for the fold as such, the same money buys support at the pyriform and medial cheek plus filler under the crease, with a year of evidence behind every syringe.
I lost weight and my folds got much deeper. Will they recover?
Partly; replace volume
I lost weight and my folds got much deeper. Will they recover?
Partly; replace volume
Facial fat leaves with body fat, including the deep fat that props the cheek forward of the seam; losing more than 10% of body weight after 45 deepens the folds markedly, and after massive weight loss blinded raters judged faces about five years older, the mid-cheek losing the most fat. Regaining weight refills the superficial fat unevenly and is the wrong fix. The right one is to keep the weight off and put the volume back where it came from: deep medial cheek and pyriform support with hyaluronic acid or a collagen stimulator, and for large losses, fat grafting or a facelift with fat grafting. Budget for this at the end of any weight-loss programme rather than treating it as a failure of the diet.
Does sleeping on my side really matter?
Plausibly, over decades
Does sleeping on my side really matter?
Plausibly, over decades
Compression, tension and shear on a cheek pressed into a pillow for seven hours a night is a mechanical load the face carries nowhere else, and the review that named sleep wrinkles maps a distribution that follows that distortion rather than any expression, worsening with age. It has never been tested in a trial, because sleeping people do not hold positions, and it does nothing to the fat, bone and descent that make most folds. Sleep on your back if you can; buy the pillow if you like; do not expect either to move a fold that stays when you lie flat.
Is there a permanent option?
PMMA, fat, surgery
Is there a permanent option?
PMMA, fat, surgery
Three things last. PMMA–collagen is permanent and the best-followed permanent filler, with 83% satisfaction at five years and 1.7% biopsy-proven granulomas that need excision rather than an enzyme, and a face that continues to deflate and descend around a fixed volume. Fat grafting is your own tissue and lasts as long as your weight does, after a variable fraction of it survives the transfer. A facelift repositions tissue for a decade, with the fold softened rather than removed. For most faces the honest answer is the semi-permanent middle — calcium hydroxylapatite or poly-L-lactic acid every one to two years — with hyaluronic acid first to learn how the fold behaves.
How long until I see something?
Days to a year
How long until I see something?
Days to a year
Hyaluronic acid and calcium hydroxylapatite show immediately and are judged at two weeks when the swelling has gone — the moment a hyaluronic lump can still be dissolved. Poly-L-lactic acid and polycaprolactone build over six to twelve weeks and keep building for months, so a second vial is decided at three months, not three weeks. Fat is judged at three months, once the graft that will survive has declared itself. Threads and energy devices are read at two to three months as collagen forms. A facelift is swollen for weeks, presentable at a month and final at six to twelve. Photograph from below, in one light, before anything.
What is the cheapest thing that works, and the most effective?
€300 / year to €20,000
What is the cheapest thing that works, and the most effective?
€300 / year to €20,000
The ladder in euros: sunscreen, a retinoid and back-sleeping (€20–60 a month, skin only) → one syringe of hyaluronic acid under the fold (€300–600, about a year) → support first plus the fold (€800–1,500 a year, the plan most deep folds actually need) → calcium hydroxylapatite or poly-L-lactic acid for one to two years a round (€600–1,600) → fat grafting (€2,500–5,000, once or twice) → a facelift with fat grafting for a descended cheek with jowls (€8,000–20,000). Threads (€800–2,000 for months) and energy devices (€1,000–3,000 for a fifth of a fold) sit outside the ladder for this problem.
Safety
The facial artery runs under the fold, which makes it the commonest site of filler-induced skin necrosis. Choose an injector who uses a cannula and keeps hyaluronidase in the room; blanching or pain out of proportion in the hours afterwards is an emergency that afternoon.
The facial artery: why the fold is the commonest site of filler necrosis
The facial artery runs under the fold and its angular branch beside the nose; in a review of 243 ischaemia cases the nose-and-fold territories were the most injured and the facial artery was involved in 58%. Cannula, aspiration, slow small aliquots, hyaluronidase in the room.
The facial artery: why the fold is the commonest site of filler necrosis
The facial artery runs under the fold and its angular branch beside the nose; in a review of 243 ischaemia cases the nose-and-fold territories were the most injured and the facial artery was involved in 58%. Cannula, aspiration, slow small aliquots, hyaluronidase in the room.
The facial artery crosses beneath the nasolabial fold on its way to the angular artery beside the nose, at a depth that varies from person to person, which is why the fold is the classic site of filler-induced skin necrosis: a systematic review of 243 ischaemia cases with 738 photographs found the frontonasal and angulonasal territories the most commonly injured and the facial artery involved in 58% of cases, with the ophthalmic artery in 48% (PRS, 2023); a nasal-ala necrosis after fold injection is the textbook case (case report). Blindness is rarer here than at the nose and glabella, but the fold is a moderate-risk site in the ophthalmology report because the angular artery connects to the eye's circulation, and vision loss occurred in 39% of the cases where that circulation was involved (AAO 2025; guideline).
The numbers that reassure: a large practitioner survey puts occlusion at about 1 in 6,410 needle syringes and 1 in 40,882 by cannula (practitioner survey), and 84% of pooled hyaluronic-acid occlusions recover at least partly with prompt hyaluronidase, delay beyond days predicting permanent damage (pooled analysis). Blanching, mottling or pain out of proportion in the hours after treatment is an emergency that afternoon, not a message left for the morning. The filler guide covers the protocol.
The stimulators and the permanent: nodules, granulomas, no eraser
PLLA nodules, CaHA lumps and PMMA granulomas (1.7% at five years) share one property — hyaluronidase does nothing for them. Delayed nodules are reported after 0.02–4.25% of hyaluronic filler treatments; with a permanent one they can arrive years later.
The stimulators and the permanent: nodules, granulomas, no eraser
PLLA nodules, CaHA lumps and PMMA granulomas (1.7% at five years) share one property — hyaluronidase does nothing for them. Delayed nodules are reported after 0.02–4.25% of hyaluronic filler treatments; with a permanent one they can arrive years later.
Everything on this page except hyaluronic acid is irreversible in the chair. Poly-L-lactic acid produces papules and nodules when placed too superficially or massaged too little; calcium hydroxylapatite lumps in thin skin and has no dissolving enzyme; PMMA carried biopsy-confirmed granulomas in 1.7% of 1,008 patients over five years, and a granuloma around permanent microspheres is excised, not injected away (five-year study). Delayed-onset nodules are reported after 0.02–4.25% of hyaluronic filler treatments, the top of the range with some lower-molecular-weight gels, sometimes after an infection or a vaccine (review). Start with what dissolves; graduate to what lasts only in a fold whose behaviour under gel you already know.
The flattened fold and the heavy upper lip
A fold filled flat reads as a long, heavy upper lip and a "pillow face", and hyaluronic gel persists for years on MRI, so annual top-ups accumulate. Fill behind the fold, leave a fold, photograph before every syringe.
The flattened fold and the heavy upper lip
A fold filled flat reads as a long, heavy upper lip and a "pillow face", and hyaluronic gel persists for years on MRI, so annual top-ups accumulate. Fill behind the fold, leave a fold, photograph before every syringe.
The commonest harm here is not a complication but a look. The fold is a normal feature of a face, and the injector who fills it flat produces a smooth slab from nose to mouth that reads as a long, heavy upper lip and, with the cheeks done to match, the swollen "facial overfilled syndrome" (overfilled syndrome). MRI shows hyaluronic gel persisting for years rather than the months of folklore, so routine annual top-ups accumulate rather than replace (MRI review). The rules are support first, a little in the fold, a visible fold left behind, and a photograph before every syringe — and hyaluronidase for the slab already there.
Threads, devices and surgery: what goes wrong
Threads dimple, show and extrude; ultrasound and radiofrequency can burn and melt cheek fat; a facelift carries nerve injury, haematoma and a scar, for a fold it may not change. Match the risk to the type of fold, not to the sales pitch.
Threads, devices and surgery: what goes wrong
Threads dimple, show and extrude; ultrasound and radiofrequency can burn and melt cheek fat; a facelift carries nerve injury, haematoma and a scar, for a fold it may not change. Match the risk to the type of fold, not to the sales pitch.
Threads under a cheek produce puckering and dimpling that usually settle in weeks, palpable or visible threads that sometimes do not, and occasional extrusion or infection; the systematic review that calls them scarcely studied also finds their complications under-reported (systematic review). Microfocused ultrasound and radiofrequency can burn, and can shrink the very cheek fat a deflated midface cannot spare; the FDA's alert on radiofrequency microneedling burns and scars is recent (FDA alert). A facelift carries haematoma, facial-nerve weakness that is usually temporary and occasionally not, and scars around the ear, for an operation whose effect on the fold the surgical literature itself calls inconsistent. The fold is the wrong reason to accept any of these; jowls and a neck are the right ones, with the fold as a bonus.
Educational content, not medical advice. The facial artery runs under this fold — filler here belongs to a trained injector with a cannula and hyaluronidase in the room, and the fold itself should be supported and softened, never filled flat.