Wrinkles · what the trials actually did
Most wrinkle creams are treating the wrong kind of line.
For women who would rather fix the right line than buy another cream.
Every treatment graded on its own trials, sorted by the kind of line it reaches.
Sound familiar?
- The line between your brows is still there after a good night's sleep.
- Foundation catches in fine lines around your eyes that were not there two years ago.
- Your expensive cream has done nothing for the lines from your nose to your mouth.
Start here
What a wrinkle actually is
A groove where the dermis has lost collagen and elastic fibres and the skin above it has thinned — surface lines live in the epidermis and upper dermis, deep ones in the dermis, folds beneath it.
What a wrinkle actually is
A groove where the dermis has lost collagen and elastic fibres and the skin above it has thinned — surface lines live in the epidermis and upper dermis, deep ones in the dermis, folds beneath it.
Skin is a two-layer laminate: a thin epidermis over a thick dermis of collagen and elastic fibres. Young dermis is dense and springs back; aged dermis has less collagen, fragmented elastin and more disorganised fibres, so a crease pressed into it — by a muscle, a pillow or a lifetime of squinting — stays. The visible groove is the epidermis following that weakened dermis down (review).
Depth decides the treatment. Fine surface lines and crepey texture are epidermal and upper-dermal, which is why tretinoin, acids and superficial resurfacing reach them. Etched expression lines run through the dermis, which is why they need a muscle relaxant to stop the folding and a laser or peel to rebuild the floor. Folds — nose to mouth, mouth to chin — are not wrinkles at all: they are the edge of a deflating, descending face, which is why filler and not skincare answers them.
When lines start, and who gets them first
In European women wrinkles and sagging start as early as the late twenties; photodamage is present in 80–90% of fair-skinned adults; darker skin wrinkles later; women get more lip lines than men.
When lines start, and who gets them first
In European women wrinkles and sagging start as early as the late twenties; photodamage is present in 80–90% of fair-skinned adults; darker skin wrinkles later; women get more lip lines than men.
In a comparison of women across five ethnic groups, wrinkles, sagging and visible vessels appeared earliest and most severely in European women — from the late twenties onward — while pigmentation appeared first in Chinese women, in whom wrinkling was not prominent until about 50 (2024 study). Photodamage of some degree is present in 80–90% of fair-skinned adults in Europe and North America (review). Vertical lip lines are strongly associated with being female, with age and with smoking — women's perioral skin has far fewer oil glands to cushion it (JAAD, 2016).
The genetics matter less than people assume. In the classic identical-twin studies, the twin who smoked, sunbathed or weighed less in later life looked years older than the sibling with the same DNA; a five-year difference in smoking history was visible on the face (smoking twins; Guyuron 2009, 186 pairs).
Why prevention beats repair, in numbers
Daily sunscreen cut measured skin aging by 24% over 4.5 years in 903 adults; nothing that repairs a wrinkle later comes close per euro.
Why prevention beats repair, in numbers
Daily sunscreen cut measured skin aging by 24% over 4.5 years in 903 adults; nothing that repairs a wrinkle later comes close per euro.
The single best trial in cosmetic dermatology is not about a treatment. In Nambour, Australia, 903 adults under 55 were randomised to daily broad-spectrum sunscreen or to using it at their own discretion; after four and a half years the daily users showed no detectable increase in skin aging on silicone casts, 24% less than the discretionary group (Hughes 2013, Annals of Internal Medicine). Add a retinoid, which has decades of randomised trials showing fewer fine wrinkles over six to twelve months, and you have the whole evidence-based prevention list.
Repair is real but expensive and partial: toxin buys three to four months of a smooth glabella; filler a year of a softer fold; a laser a lasting but incomplete improvement with a week of downtime. The wrinkle you never etch costs €10 a month. Start the base now, whatever else you do.
Why it hasn't worked for you so far
Wrinkles: fixable or here to stay?
What's real: sunscreen and a retinoid soften fine lines, toxin relaxes expression lines and filler softens folds, each with randomised trials behind it. What's not: one cream for every line. Here's how to tell them apart:
-
The fold
Not a wrinkle at all
The lines from nose to mouth and mouth to chin are the edge of a deflating, descending cheek (Mendelson & Wong). No cream reaches that layer; filler or a collagen stimulator does.
-
The eye cream
A smaller jar at a higher price
No ingredient works only in an eye cream: the same retinoid, vitamin C and sunscreen work under the eyes, used more cautiously. Crow's feet are expression lines, and belong to toxin.
-
The one nobody mentions
Waiting until the line stays
Expression lines start dynamic, visible only when you frown or squint, and turn static once the skin stops springing back. Make the expression, then relax: a line that stays needs the muscle stopped and the skin treated, which is more work than catching it early.
The science
Wrinkles — what the evidence says
Every option, strongest first. Open any row for the trials behind it.
At home: what you put on your face
Strong evidence Daily broad-spectrum sunscreen
The only intervention shown in a randomised trial to slow skin aging itself: 903 adults, 4.5 years, 24% less measured skin aging with daily use versus discretionary use.
Daily broad-spectrum sunscreen
The only intervention shown in a randomised trial to slow skin aging itself: 903 adults, 4.5 years, 24% less measured skin aging with daily use versus discretionary use.
The only intervention shown in a randomised trial to slow skin aging itself: 903 adults, 4.5 years, 24% less measured skin aging with daily use versus discretionary use.
Sunscreen is the only anti-wrinkle intervention proven in a randomised trial to slow aging itself. In the Nambour trial, adults under 55 assigned to daily broad-spectrum SPF 15+ showed no detectable increase in skin aging over 4.5 years on silicone skin casts — 24% less aging than those using sunscreen when they felt like it (Hughes 2013). Photodamage is present in 80–90% of fair-skinned adults, and UV is the largest single cause of the collagen breakdown that makes wrinkles (review).
Practicalities: SPF 30–50, broad-spectrum (UVA is the wrinkle wavelength, and the EU's UVA seal or PA rating matters more than the SPF number), a quarter-teaspoon for the face, every day including winter and indoors near windows, reapplied when outdoors. Mineral or chemical filters both work; the one you will actually wear is the right one. Sunscreen does not undo existing lines — it stops the next ones.
- Best for
- everyone — the base under every other line on this page
- Sessions
- Every morning, reapplied outdoors
- Downtime
- None
- Cost
- €10–30 / month
Our pick
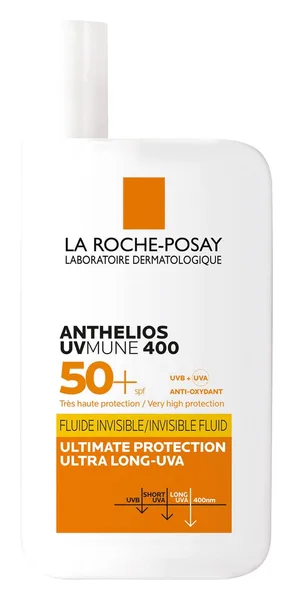
La Roche-Posay Anthelios UVMune 400 Invisible Fluid SPF50+ — the unperfumed version: a water-resistant SPF 50+ fluid from a European pharmacy brand, with Mexoryl 400 for the longest UVA rays; 50 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
Strong evidence Tretinoin (prescription retinoid)
Decades of randomised trials: fewer fine wrinkles, smoother texture and more dermal collagen over 6–12 months; the meta-analysis confirms it. The one cream that changes the dermis.
Tretinoin (prescription retinoid)
Decades of randomised trials: fewer fine wrinkles, smoother texture and more dermal collagen over 6–12 months; the meta-analysis confirms it. The one cream that changes the dermis.
Decades of randomised trials: fewer fine wrinkles, smoother texture and more dermal collagen over 6–12 months; the meta-analysis confirms it. The one cream that changes the dermis.
Tretinoin is the reference anti-wrinkle molecule because it is the one that has been tested properly. Two 24-week randomised, vehicle-controlled trials in 533 people found 0.05% emollient cream reduced fine wrinkling, roughness, mottled pigmentation and laxity (overview); 48-week multicentre trials confirmed continued improvement (48-week studies); even 0.02% worked in two double-blind studies (0.02% cream); and a systematic review and meta-analysis of the randomised trials pools the effect (meta-analysis). Biopsies show the mechanism — thicker epidermis, new collagen in the upper dermis, reorganised elastic fibres.
The catch is tolerance: dryness, redness and flaking for the first six to eight weeks, which is why most people quit. Start 0.025% two or three nights a week on dry skin over a moisturiser, build to nightly, and expect visible change at three to four months and the full effect at a year. Not in pregnancy; always with sunscreen. Adapalene 0.3% was non-inferior to tretinoin 0.05% in one comparison and is gentler (comparison).
- Best for
- fine lines, crepey texture and prevention — the second half of the base
- Sessions
- Nightly (start 2–3× a week), indefinitely
- Downtime
- Weeks 1–8: dryness, flaking
- Cost
- €10–30 / month
Strong evidence Collagen peptide supplements
Pooled trials show better hydration, elasticity and wrinkle depth over 8–12 weeks; a 2025 meta-analysis that found none in the independent trials leaned on low doses and forearm skin. Take 10 g a day with vitamin C, alongside a retinoid.
Collagen peptide supplements
Pooled trials show better hydration, elasticity and wrinkle depth over 8–12 weeks; a 2025 meta-analysis that found none in the independent trials leaned on low doses and forearm skin. Take 10 g a day with vitamin C, alongside a retinoid.
Pooled trials show better hydration, elasticity and wrinkle depth over 8–12 weeks; a 2025 meta-analysis that found none in the independent trials leaned on low doses and forearm skin. Take 10 g a day with vitamin C, alongside a retinoid.
Oral collagen peptides are absorbed as small fragments that appear to signal fibroblasts. A 2019 systematic review of 11 studies in 805 people found that oral collagen increased skin elasticity, hydration and dermal collagen density — "Preliminary results are promising" (2019 systematic review) — and a 2025 meta-analysis of 23 randomised trials found significant gains in hydration, elasticity and wrinkles across all of them (2025 meta-analysis). Its conclusion that there is "no clinical evidence" goes too far: it rests on the few trials without pharmaceutical-company funding, two of which gave only 1–2 g a day, and the clearest negative trial measured forearm skin in women aged 60 to 93 with fragile, thinning skin (our reading of it). Most trials are funded by the makers, and the effects are the kind you measure with an instrument rather than see across a room.
Take about 10 g a day with vitamin C and other skin nutrients. The skin may also need a local signal to build collagen where the lines are: a nightly retinoid or a collagen-stimulating treatment. Collagen alone at a low dose may not be enough. Our collagen guide grades the forms and doses; the honest summary is "real, small, and best on top of a retinoid".
- Sessions
- 10 g daily with vitamin C, 8–12 weeks to judge
- Downtime
- None
- Cost
- €25–50 / month

Our pick
Aeterna COLLAGEN MAX PRO — 10 g of Peptan® collagen peptides per 13 g scoop, with a hyaluronic-acid matrix, plant ceramides and acerola vitamin C. Bovine, or fish in the Marin C+ version.
See the product Label facts, prices, the evidence graded.
Moderate evidence Retinol and retinal (over-the-counter retinoids)
Real but weaker cousins: 0.4% retinol improved fine wrinkles and collagen in older skin; well-formulated retinol products approached tretinoin in split-face comparisons; retinaldehyde matched a course of glycolic peels.
Retinol and retinal (over-the-counter retinoids)
Real but weaker cousins: 0.4% retinol improved fine wrinkles and collagen in older skin; well-formulated retinol products approached tretinoin in split-face comparisons; retinaldehyde matched a course of glycolic peels.
Real but weaker cousins: 0.4% retinol improved fine wrinkles and collagen in older skin; well-formulated retinol products approached tretinoin in split-face comparisons; retinaldehyde matched a course of glycolic peels.
Retinol has to be converted twice in the skin to become tretinoin, so it is weaker gram for gram but far better tolerated. The evidence is real: in the classic study, 0.4% retinol applied to one arm of older adults up to three times a week for 24 weeks reduced fine wrinkles and increased collagen and glycosaminoglycan production on biopsy (Kafi 2007); 0.3% retinol improved multiple photoaging measures in a later study (2022 study); and in a randomised split-face comparison, a well-formulated retinol regimen approached the tretinoin regimen on wrinkle scores with less irritation (split-face study). Retinaldehyde, one step closer to tretinoin, matched a course of glycolic peels in a randomised study (2018 trial).
What to buy: a stated concentration (retinol up to 0.3%, the EU limit for face products, or 0.05–0.1% retinaldehyde), airless opaque packaging (retinoids oxidise), and patience — the trials ran 24 weeks. Most "retinol" products list no percentage and contain a token amount.
- Best for
- skin that cannot tolerate tretinoin, and prevention from the late twenties
- Sessions
- Nightly, indefinitely
- Downtime
- Mild dryness in weeks 1–4
- Cost
- €15–60 / month

Our pick
La Roche-Posay Retinol B3 Serum — 0.3% retinol — 0.1% pure and 0.2% gradual-release, the EU limit for the face — with 2% niacinamide, made for sensitive skin; 30 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.

Moderate evidence Vitamin C (L-ascorbic acid) serum
Two small double-blind trials: 5% for six months reduced deep furrows and improved surface microrelief; a 12-week half-face study showed new collagen on biopsy. Modest, real, unstable in the bottle.
Vitamin C (L-ascorbic acid) serum
Two small double-blind trials: 5% for six months reduced deep furrows and improved surface microrelief; a 12-week half-face study showed new collagen on biopsy. Modest, real, unstable in the bottle.
Two small double-blind trials: 5% for six months reduced deep furrows and improved surface microrelief; a 12-week half-face study showed new collagen on biopsy. Modest, real, unstable in the bottle.
Vitamin C is a cofactor for collagen synthesis and an antioxidant that mops up the free radicals UV generates. Topically, the evidence is small but controlled: in a six-month double-blind, randomised trial, a 5% cream significantly reduced deep furrows and increased the density of skin microrelief on the treated side (Humbert 2003); an earlier 12-week double-blind half-face study found clinically visible improvement in wrinkling with biopsy evidence of new collagen (Fitzpatrick 2002). Combined with vitamin E and ferulic acid it also measurably reduces UV damage under sunscreen, which is its most defensible job.
The practical problem is chemistry: L-ascorbic acid oxidises in weeks once opened and goes yellow-brown. Buy 10–20% in opaque, airless packaging, keep it cool, and discard when it darkens. Derivatives are stabler and weaker.
- Best for
- a morning antioxidant layer under sunscreen
- Sessions
- Every morning
- Downtime
- None (stinging at 15–20%)
- Cost
- €20–80 / month
Our pick
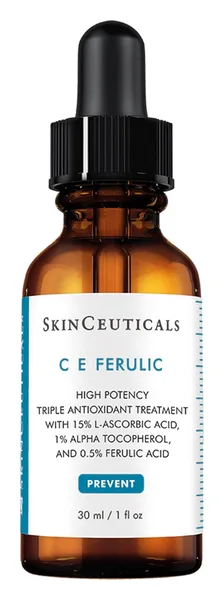
SkinCeuticals C E Ferulic — 15% L-ascorbic acid with 1% vitamin E and 0.5% ferulic acid, the combination tested in the photoprotection studies, in a dark glass bottle; 30 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
Moderate evidence Niacinamide 4–5%
A 12-week double-blind split-face RCT in 50 women: fewer fine lines and wrinkles, less blotchiness, better elasticity. Cheap, gentle, and modest.
Niacinamide 4–5%
A 12-week double-blind split-face RCT in 50 women: fewer fine lines and wrinkles, less blotchiness, better elasticity. Cheap, gentle, and modest.
A 12-week double-blind split-face RCT in 50 women: fewer fine lines and wrinkles, less blotchiness, better elasticity. Cheap, gentle, and modest.
Niacinamide (vitamin B3) supports the skin barrier, calms inflammation and reduces pigment transfer. In the best study, 50 women applied 5% niacinamide to one side of the face and vehicle to the other, twice daily for 12 weeks, double-blind: the niacinamide side showed significant reductions in fine lines and wrinkles, hyperpigmented spots, red blotchiness and sallowness, and improved elasticity on cutometry (Bissett 2005). A cosmetic regimen of niacinamide, peptides and retinyl propionate was comparable to 0.02% tretinoin for wrinkles in a randomised comparison — a fair statement of its ceiling (regimen trial). The 4–5% concentration in the trials is the useful dose; the 10% versions add irritation, not effect.
- Sessions
- Once or twice daily
- Downtime
- None
- Cost
- €10–30 / month

Our pick
The Ordinary Niacinamide 5% Face and Body Emulsion — 5% niacinamide, the strength of the trials, in a light moisturiser for face and body; 100 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
Moderate evidence Hyaluronic-acid serums and moisturisers
Reduce the look of fine and coarse lines within minutes to hours by hydrating and plumping the surface — measurable in trials, gone when you stop. Cosmetic, not corrective.
Hyaluronic-acid serums and moisturisers
Reduce the look of fine and coarse lines within minutes to hours by hydrating and plumping the surface — measurable in trials, gone when you stop. Cosmetic, not corrective.
Reduce the look of fine and coarse lines within minutes to hours by hydrating and plumping the surface — measurable in trials, gone when you stop. Cosmetic, not corrective.
Dehydrated skin creases more, and hydrating it uncreases it — for as long as it stays hydrated. A serum with five forms of hyaluronic acid produced statistically significant reductions in fine and coarse lines and roughness immediately after application, with cumulative improvement over weeks of use (JAAD, 2016); a 2023 review of topical hyaluronic acid reaches the same conclusion about hydration and the appearance of aging (review). Topical hyaluronic acid does not penetrate to the dermis and does not build anything; it holds water in the surface, which is exactly what makes a fine line look shallower at 9 a.m.
Use it for what it does: instant softening, a comfortable buffer under tretinoin, and better barrier function in dry or menopausal skin. Any moisturiser with glycerin and ceramides does most of the same — see the ceramides guide.
- Best for
- the instant, temporary softening of fine lines — and as the buffer under a retinoid
- Sessions
- Twice daily
- Downtime
- None
- Cost
- €10–60 / month
Our pick
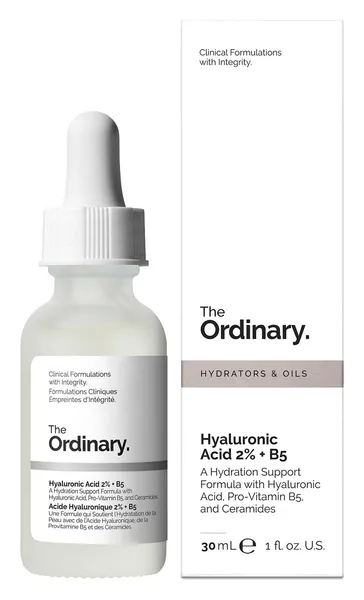
The Ordinary Hyaluronic Acid 2% + B5 — hyaluronic acid in several molecular weights with pro-vitamin B5, now with ceramides — the inexpensive bottle the row says does the job; 30 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
Moderate evidence Not smoking, less sugar, enough sleep
Identical-twin studies make smoking the best-documented avoidable wrinkle cause; glycation and poor sleep are mechanistically sound with observational support. No trial can randomise a cigarette.
Not smoking, less sugar, enough sleep
Identical-twin studies make smoking the best-documented avoidable wrinkle cause; glycation and poor sleep are mechanistically sound with observational support. No trial can randomise a cigarette.
Identical-twin studies make smoking the best-documented avoidable wrinkle cause; glycation and poor sleep are mechanistically sound with observational support. No trial can randomise a cigarette.
Smoking is the cleanest case: among 79 pairs of identical twins discordant for smoking, the smoker scored worse for upper-lip lines, lower-lid bags, nasolabial folds and jowls, and five years of smoking difference was visible on the face (twin study); the larger Guyuron twin series added sun, alcohol and weight swings to the list (Guyuron 2009). Sugar ages skin by glycation — sugars cross-link collagen and elastin into stiff, brittle fibres — which is well established mechanistically and supported by observational data, not trials (review). Poor sleepers showed more intrinsic aging signs and slower barrier recovery in a 60-woman study (Oyetakin-White 2015).
None of this reverses a line. All of it decides how many you make in the next decade, at zero cost.
- Sessions
- Ongoing
- Downtime
- None
- Cost
- Free
Emerging evidence Glycolic and lactic acid (AHAs)
One 22-week double-blind trial: 76% of women on 8% glycolic and 71% on 8% lactic improved at least one photodamage grade versus 40% on vehicle. Surface smoothing, not dermal repair.
Glycolic and lactic acid (AHAs)
One 22-week double-blind trial: 76% of women on 8% glycolic and 71% on 8% lactic improved at least one photodamage grade versus 40% on vehicle. Surface smoothing, not dermal repair.
One 22-week double-blind trial: 76% of women on 8% glycolic and 71% on 8% lactic improved at least one photodamage grade versus 40% on vehicle. Surface smoothing, not dermal repair.
Alpha-hydroxy acids loosen the bonds between dead surface cells, which smooths texture and brightens within weeks; at higher concentrations and over months they modestly thicken the epidermis. The controlled evidence is one good trial: 74 women aged 40–70 used 8% glycolic acid, 8% lactic acid or vehicle for 22 weeks, and the proportion improving by at least one grade of photodamage was 76%, 71% and 40% respectively (Stiller 1996). A daily 5% glycolic formulation showed only trends toward improvement in a smaller double-blind study (1998 trial).
Useful for texture and dullness, less so for a wrinkle you can feel. They increase sun sensitivity — sunscreen is non-negotiable — and they compete with retinoids for the same irritation budget, so alternate nights rather than layering. Our peel guide covers the in-clinic strengths.
- Sessions
- 2–7 nights a week
- Downtime
- Stinging; sun sensitivity
- Cost
- €10–40 / month
Emerging evidence Bakuchiol
One 44-person, 12-week randomised double-blind trial: 0.5% bakuchiol matched 0.5% retinol on wrinkle area and pigment with less scaling and stinging. Promising, single-study.
Bakuchiol
One 44-person, 12-week randomised double-blind trial: 0.5% bakuchiol matched 0.5% retinol on wrinkle area and pigment with less scaling and stinging. Promising, single-study.
One 44-person, 12-week randomised double-blind trial: 0.5% bakuchiol matched 0.5% retinol on wrinkle area and pigment with less scaling and stinging. Promising, single-study.
Bakuchiol is a plant compound with retinoid-like gene effects and none of the retinoid chemistry, which is why it is marketed as "retinol for sensitive skin". The evidence is one well-designed trial: 44 people randomised to 0.5% bakuchiol twice daily or 0.5% retinol nightly for 12 weeks, double-blind, with computer-analysed photographs. Both reduced wrinkle surface area and pigmentation with no statistical difference between them, and the retinol group reported more scaling and stinging (Dhaliwal 2019, BJD). One trial against a modest comparator makes it emerging, not proven — but it is the only "natural retinol" with a randomised trial behind it, and it can be used in pregnancy, where retinoids cannot.
- Sessions
- Twice daily (trial regimen)
- Downtime
- None
- Cost
- €20–50 / month
Emerging evidence Peptides (Matrixyl, argireline and friends)
Signal peptides have small manufacturer trials and a place in one regimen that rivalled 0.02% tretinoin; the "Botox in a bottle" hexapeptide has never been tested against toxin. Pleasant, modest, over-marketed.
Peptides (Matrixyl, argireline and friends)
Signal peptides have small manufacturer trials and a place in one regimen that rivalled 0.02% tretinoin; the "Botox in a bottle" hexapeptide has never been tested against toxin. Pleasant, modest, over-marketed.
Signal peptides have small manufacturer trials and a place in one regimen that rivalled 0.02% tretinoin; the "Botox in a bottle" hexapeptide has never been tested against toxin. Pleasant, modest, over-marketed.
Peptides are fragments of collagen or nerve-signalling proteins that, in cell culture, nudge fibroblasts to make matrix or dampen the muscle signal. The clinical evidence is thin and mostly manufacturer-run. Palmitoyl pentapeptide (Matrixyl) was part of a niacinamide-and-retinyl-propionate regimen that matched 0.02% tretinoin for wrinkle reduction in a randomised comparison (regimen trial), and a multi-peptide eye serum improved crow's feet measures in a 2023 controlled study (2023 trial). Acetyl hexapeptide-3 (argireline), sold as "Botox in a bottle", relaxes muscle in a dish; it has never been compared with toxin in a controlled trial, and a topical cannot reach the muscle that makes a frown line.
Verdict: fine in a moisturiser you like, priced as if they were prescriptions. If a peptide product costs more than tretinoin and sunscreen together, the money is in the wrong place.
- Sessions
- Daily
- Downtime
- None
- Cost
- €20–120 / month
Emerging evidence Growth-factor and "stem-cell" serums
A cosmetic growth-factor serum beat placebo on fine and coarse lines in a 12-week trial and a 2023 systematic review is cautiously positive; "stem-cell" creams contain no stem cells and lean on conditioned-medium studies.
Growth-factor and "stem-cell" serums
A cosmetic growth-factor serum beat placebo on fine and coarse lines in a 12-week trial and a 2023 systematic review is cautiously positive; "stem-cell" creams contain no stem cells and lean on conditioned-medium studies.
A cosmetic growth-factor serum beat placebo on fine and coarse lines in a 12-week trial and a 2023 systematic review is cautiously positive; "stem-cell" creams contain no stem cells and lean on conditioned-medium studies.
Growth-factor serums contain signalling proteins harvested from cultured cells and, in a few controlled trials, they do something: a cosmetic growth-factor serum produced significantly greater reductions in fine and coarse lines than placebo at 4, 8 and 12 weeks (JAAD, 2018), and a 2023 systematic review found most studies positive but small, short and often uncontrolled (Quinlan 2023). "Stem-cell" creams contain no living cells; the better ones use the conditioned medium those cells grew in, for which a meta-analysis of randomised trials — mostly as an add-on to lasers and needling — found reductions in wrinkles and pigment (2022 meta-analysis). Large proteins penetrate intact skin poorly, which is why the strongest data come from use after resurfacing. At €100–300 a bottle, the price is far ahead of the evidence.
- Sessions
- Twice daily
- Downtime
- None
- Cost
- €100–300 a bottle
Emerging evidence Red and near-infrared LED masks
A 2014 randomised controlled trial and a 2023 meta-analysis show modest improvements in roughness and fine lines at clinic doses; home masks deliver a fraction of that dose.
Red and near-infrared LED masks
A 2014 randomised controlled trial and a 2023 meta-analysis show modest improvements in roughness and fine lines at clinic doses; home masks deliver a fraction of that dose.
A 2014 randomised controlled trial and a 2023 meta-analysis show modest improvements in roughness and fine lines at clinic doses; home masks deliver a fraction of that dose.
Red (630–660 nm) and near-infrared light stimulate fibroblast metabolism in a dish, and in people the controlled evidence is real but modest. The reference trial randomised 113 of 136 people to red/near-infrared light twice weekly for 30 sessions and compared them with 23 untreated controls: treated skin showed significantly improved complexion, roughness and collagen density on ultrasound (Wunsch & Matuschka 2014); a 2023 meta-analysis of LED skin therapy found consistent skin-rejuvenation benefits across small trials with heterogeneous devices and doses (2023 meta-analysis). Consumer masks emit a fraction of the irradiance used in trials and there is no head-to-head against a retinoid. Harmless, pleasant, and the least cost-effective item on this list. Our red-light guide covers doses.
- Sessions
- 3–5× a week, 10–20 min
- Downtime
- None
- Cost
- €200–500 device
Limited evidence Silicone patches and face tape
Silicone patches have no trial and soften a crease briefly by hydration and by stopping the fold overnight. Adhesive tape pads smoothed crow's feet for about an hour in a placebo-controlled study and did nothing measurable for forehead lines in four weeks.
Silicone patches and face tape
Silicone patches have no trial and soften a crease briefly by hydration and by stopping the fold overnight. Adhesive tape pads smoothed crow's feet for about an hour in a placebo-controlled study and did nothing measurable for forehead lines in four weeks.
Silicone patches have no trial and soften a crease briefly by hydration and by stopping the fold overnight. Adhesive tape pads smoothed crow's feet for about an hour in a placebo-controlled study and did nothing measurable for forehead lines in four weeks.
Silicone patches hold moisture against the skin and physically prevent the crease from forming while you sleep, so a forehead or chest line looks softer for a short while after removal — the same mechanism as a hydrating serum, plus splinting; on the forearm, the water a silicone sheet adds to the skin is lost quickly once it comes off (Suetak 2000). We found no trial of a silicone wrinkle patch in PubMed (searched October 2026). Adhesive tape pads have been tested: on crow's feet, a placebo-controlled study found they smoothed the skin "in the first hour after use" and were "tolerable for most users" (Mazzarello 2018), and on forehead and frown lines four weeks of nightly use gave "no statistical benefit" on blinded rating (Ryan 2009). No study has shown an effect that outlasts the first hour after removal, and neither product relaxes the muscle. Cheap experiments for sleep creases and chest lines; not treatments.
- Sessions
- Nightly
- Downtime
- None
- Cost
- €15–40
Limited evidence Facial exercise and "face yoga"
A 16-woman uncontrolled pilot found fuller cheeks and a perceived age three years younger after 20 weeks; nothing on wrinkles, and repeated expression is how expression lines form.
Facial exercise and "face yoga"
A 16-woman uncontrolled pilot found fuller cheeks and a perceived age three years younger after 20 weeks; nothing on wrinkles, and repeated expression is how expression lines form.
A 16-woman uncontrolled pilot found fuller cheeks and a perceived age three years younger after 20 weeks; nothing on wrinkles, and repeated expression is how expression lines form.
The study everyone cites enrolled 27 women aged 40–65 in a 20-week programme of 30-minute daily facial exercises; the 16 who finished were rated as having fuller upper and lower cheeks, and blinded estimated age fell from 50.8 to 48.1 years (Alam 2018, JAMA Dermatology). It had no control group, measured fullness rather than lines, and the effect could plausibly be hypertrophy of the cheek muscles. For wrinkles specifically the logic runs the other way: expression lines are made by repeated contraction, and dermatologists who inject toxin spend their days stopping exactly the movements face yoga prescribes. Harmless for cheeks; unproven for anything else.
- Sessions
- 30 min daily (pilot regimen)
- Downtime
- None
- Cost
- Free
Injectables
Strong evidence Botulinum toxin for expression lines
The pivotal glabellar trial: 77–89% responders at day 30 versus placebo; crow’s feet 55% vs 3%; forehead 46–53% vs 0.6%. Three to four months a dose, the most-studied cosmetic treatment there is.
Botulinum toxin for expression lines
The pivotal glabellar trial: 77–89% responders at day 30 versus placebo; crow’s feet 55% vs 3%; forehead 46–53% vs 0.6%. Three to four months a dose, the most-studied cosmetic treatment there is.
The pivotal glabellar trial: 77–89% responders at day 30 versus placebo; crow’s feet 55% vs 3%; forehead 46–53% vs 0.6%. Three to four months a dose, the most-studied cosmetic treatment there is.
Botulinum toxin blocks the nerve signal to the small muscles that fold the skin, and for the lines they make it is the treatment. In the pivotal placebo-controlled glabellar trial, 20 units across five sites produced a responder rate at day 30 of 77% by physician rating at maximal frown and 89% by patient assessment, against near-zero for placebo, with adverse events no different from placebo (Carruthers 2003). For crow's feet the phase 3 responder rate was 55% (investigator) versus 3% for placebo (phase 3); for forehead lines, 46–53% improved by two grades versus 0.6% (review); a combined upper-face protocol keeps patients satisfied for up to six months (2022 study). Newer toxins (abo-, inco-, pra-, dax-) are equivalent or slightly longer-lasting.
What it does not do: it does not fill a static groove that has already etched in — that softens over repeated cycles as the dermis recovers, or needs resurfacing; and it does nothing for folds or lip volume. Dose and placement decide the look: a light dose keeps movement, a heavy one freezes. Effect starts at day 3–5, peaks at two weeks and fades at three to four months, with no cumulative harm from stopping. Our 40s guide covers the toxin-and-filler decade in context.
- Best for
- frown lines, crow’s feet and forehead lines — dynamic first, static with time
- Sessions
- Every 3–4 months
- Downtime
- None; bruise possible
- Cost
- €200–400 per area

Available at a partner clinic
EGP Aesthetics — offers this after a consultation. It is a prescription-only treatment, so no price or online booking is shown here. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Strong evidence Hyaluronic-acid filler for folds
Randomised trials with blinded graders: about 80% of patients still had folds at least a grade better at 12 months; reversible with hyaluronidase.
Hyaluronic-acid filler for folds
Randomised trials with blinded graders: about 80% of patients still had folds at least a grade better at 12 months; reversible with hyaluronidase.
Randomised trials with blinded graders: about 80% of patients still had folds at least a grade better at 12 months; reversible with hyaluronidase.
Folds are volume problems, and hyaluronic-acid gel replaces volume. The evidence base is unusually good because regulators demand it: in two randomised split-face pivotal trials, responder rates on the Wrinkle Severity Rating Scale (at least one grade better) were 81% at two weeks and 56% at 26 weeks for both the test gel and the Restylane comparator (two RCTs); in a 12-month randomised comparison of two gels, about 80% of subjects were still responders at a year (12-month trial); a 52-week split-face study found the same (52-week study). MRI studies show the gel persists far longer than the "six months" folklore, which is the argument against topping up on a schedule (MRI review).
The skilled version treats the cause — the deflated cheek — rather than the fold, which is why an injector who reaches for the cheekbone when you ask about the nasolabial line is usually the better one. Risks are rare but real (vascular occlusion, blindness) and covered in the safety drawer; the gel dissolves on demand with hyaluronidase. Our filler guide goes zone by zone.
- Best for
- nasolabial and marionette folds — or the deflated cheek that causes them
- Sessions
- Every 9–18 months
- Downtime
- 1–3 days of swelling; bruising
- Cost
- €300–600 per syringe
Available at a partner clinic
EGP Aesthetics — Full Face Balancing (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £790, 90 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Thin fillers for fine and lip lines
Low-viscosity gels (Volbella, Kysse) soften perioral lines and fine cheek lines with pivotal-trial support in the lips; skin boosters, a different idea, improve hydration and roughness for 3–6 months.
Thin fillers for fine and lip lines
Low-viscosity gels (Volbella, Kysse) soften perioral lines and fine cheek lines with pivotal-trial support in the lips; skin boosters, a different idea, improve hydration and roughness for 3–6 months.
Low-viscosity gels (Volbella, Kysse) soften perioral lines and fine cheek lines with pivotal-trial support in the lips; skin boosters, a different idea, improve hydration and roughness for 3–6 months.
Soft, low-viscosity hyaluronic-acid gels placed superficially or in the lip fill the deepest perioral grooves and add the small volume whose loss slackens the skin above the lip. The pivotal trial for Volbella in the lips and perioral area showed responder rates sustained to a year (Volbella pivotal trial). Microdroplet "skin boosters" (Restylane Vital) are a different idea — hydration and roughness rather than filling — and in a randomised, open-label, single-centre study of two against three initial sessions, 72–79% of patients rated themselves improved at three months and investigators rated 92–96% improved (randomised study); with Juvéderm Volite, a similar skin-quality gel, the skin-roughness responder rate fell from 96% at month one to 35% by month six in a single-arm study (responder data). Profhilo, the "bioremodelling" injectable, has thinner evidence than its marketing; the filler guide grades it separately.
The trade-off in the lip zone is lumps and visible product in thin skin, which is why the best results combine a small volume of thin gel with a few units of toxin and resurfacing, rather than more filler.
- Best for
- vertical lip lines and fine etched lines, alongside toxin and resurfacing
- Sessions
- Every 6–12 months
- Downtime
- 1–3 days swelling
- Cost
- €300–500 per syringe
Available at a partner clinic
EGP Aesthetics — Facial Skin Booster (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £390, 30 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Poly-L-lactic acid (Sculptra)
A collagen stimulator: randomised trials show nasolabial-fold correction lasting up to 25 months, with a double-blind 252-person trial confirming long-term effect. Slow, gradual, subtle.
Poly-L-lactic acid (Sculptra)
A collagen stimulator: randomised trials show nasolabial-fold correction lasting up to 25 months, with a double-blind 252-person trial confirming long-term effect. Slow, gradual, subtle.
A collagen stimulator: randomised trials show nasolabial-fold correction lasting up to 25 months, with a double-blind 252-person trial confirming long-term effect. Slow, gradual, subtle.
Poly-L-lactic acid microspheres are injected as a suspension and, over two to three months, provoke fibroblasts to lay down new collagen around them, so the volume that appears is the patient's own. In the randomised pivotal comparison against human collagen filler, nasolabial-fold correction was significantly better from month 3 and persisted to 25 months (FDA summary); a 2026 multicentre, double-blinded, randomised trial in 252 people found 92.4% of nasolabial folds still corrected at 48 weeks against 59.3% with hyaluronic acid (2026 trial). Because the effect builds slowly it never looks "done"; because it is collagen it lasts. The price of that is patience, the need for meticulous dilution and massage to avoid nodules, and no hyaluronidase escape hatch if you dislike it.
- Best for
- diffuse deflation and folds in someone who wants gradual, long-lasting change
- Sessions
- 2–3 sessions 4–6 weeks apart; top-up at 2 years
- Downtime
- 1–2 days; nodules rare
- Cost
- €400–700 per vial
Available at a partner clinic
EGP Aesthetics — Sculptra Collagen Biostimulator (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £950, 90 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Calcium hydroxylapatite (Radiesse)
A stiffer filler that also stimulates collagen: in randomised split-face trials it outlasted a hyaluronic filler (79% of folds still improved at a year against 43%) and human collagen; not reversible.
Calcium hydroxylapatite (Radiesse)
A stiffer filler that also stimulates collagen: in randomised split-face trials it outlasted a hyaluronic filler (79% of folds still improved at a year against 43%) and human collagen; not reversible.
A stiffer filler that also stimulates collagen: in randomised split-face trials it outlasted a hyaluronic filler (79% of folds still improved at a year against 43%) and human collagen; not reversible.
Calcium hydroxylapatite is a suspension of mineral microspheres in gel; it fills immediately and stimulates collagen as the gel is absorbed, so results outlast the product. In a 60-person split-face trial against a hyaluronic filler, 79% of the calcium hydroxylapatite folds were still improved at 12 months against 43% (2008 split-face trial), and against human collagen in 117 people 79% had the better result on the calcium hydroxylapatite side at six months, with less product (2007 trial); the Radiesse guide grades it area by area. It cannot be dissolved, must not go in the lips, and diluted ("hyperdilute") it doubles as a skin-quality treatment for the cheeks and neck. A good choice for deep folds in a heavier face; a poor one for a first-time patient who might want to undo it.
- Sessions
- Every 12–18 months
- Downtime
- 1–3 days
- Cost
- €400–700 per syringe
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence PRP and PRF for facial lines
Three randomised split-face trials show modest improvement in texture and fine lines, mostly when combined with needling or laser; small, heterogeneous, protocol-dependent.
PRP and PRF for facial lines
Three randomised split-face trials show modest improvement in texture and fine lines, mostly when combined with needling or laser; small, heterogeneous, protocol-dependent.
Three randomised split-face trials show modest improvement in texture and fine lines, mostly when combined with needling or laser; small, heterogeneous, protocol-dependent.
Platelet-rich plasma injected into or needled into the face delivers growth factors that, in three randomised split-face trials, improved skin texture and fine wrinkles modestly over a few months — with the clearest effects when combined with microneedling or laser rather than alone (three split-face trials). Preparation systems, platelet concentrations and injection depths vary wildly, which keeps the tier at emerging. It is a reasonable add-on for someone already having needling, and a poor stand-alone purchase; the PRP guide covers the systems and the polynucleotide and exosome cousins.
- Sessions
- 3 sessions a month apart
- Downtime
- 1–2 days
- Cost
- €200–500 / session
Available at a partner clinic
EGP Aesthetics — PRP/PRF Stem Cells Rejuvenation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £480, 90 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Limited evidence "Preventive" or "baby" toxin in your twenties
The evidence that early toxin prevents static lines is one pair of twins; a light dose once lines appear with expression is reasonable, treating a smooth 25-year-old face is not.
"Preventive" or "baby" toxin in your twenties
The evidence that early toxin prevents static lines is one pair of twins; a light dose once lines appear with expression is reasonable, treating a smooth 25-year-old face is not.
The evidence that early toxin prevents static lines is one pair of twins; a light dose once lines appear with expression is reasonable, treating a smooth 25-year-old face is not.
The idea is sound — stop the folding before the crease etches — and the evidence is a single case report: identical twins, one treated with toxin two to three times a year for 13 years, the other twice in total, with the treated twin showing no forehead or glabellar lines at rest and the untreated twin visible ones (Binder's twins). One pair is not a trial. The sensible reading: once a line appears with expression and is starting to persist at rest — typically late twenties to thirties — a light dose is prevention with a plausible mechanism. Injecting a face that has no lines at rest is a subscription, not a treatment. Our 30s guide takes the prejuvenation industry apart in detail.
- Sessions
- Every 4–6 months
- Downtime
- None
- Cost
- €200–350 per session
Resurfacing and devices
Strong evidence Ablative lasers (fractional CO₂, erbium)
The most effective wrinkle treatment short of a deep peel: randomised split-face trials for periorbital lines, decades of series for perioral lines, results that last years — with a week of downtime and real pigment risk.
Ablative lasers (fractional CO₂, erbium)
The most effective wrinkle treatment short of a deep peel: randomised split-face trials for periorbital lines, decades of series for perioral lines, results that last years — with a week of downtime and real pigment risk.
The most effective wrinkle treatment short of a deep peel: randomised split-face trials for periorbital lines, decades of series for perioral lines, results that last years — with a week of downtime and real pigment risk.
Ablative lasers vaporise the epidermis and heat the dermis; the skin that regrows is thicker, with new organised collagen. Full-field CO₂ resurfacing produced wrinkle improvement persisting for years in the classic series (long-term follow-up) at the price of prolonged redness and delayed hypopigmentation in about 8% (1999 series), which is why fractional delivery — columns of injury with intact skin between, introduced in 2004 and soon applied to ablative lasers — took over (original paper). For periorbital wrinkles a randomised split-face trial of fractional CO₂ showed significant improvement with a tolerable protocol (2025 RCT); a prospective study found half of patients holding 26–50% improvement at a year (12-month study); fractional erbium improves periorbital and perioral lines with age and smoking predicting response (2021 study). A 16-study systematic review supports the class for photoaging (systematic review).
The trade is downtime and risk: a week of open, weeping skin, weeks of pink, post-inflammatory hyperpigmentation in darker skin (even a gentler non-ablative laser darkened about 4% of sessions in Fitzpatrick IV–VI, series), and cold-sore reactivation unless prophylaxed (study). Our laser guide walks the ladder from gentle to full ablation.
- Best for
- etched crow’s feet, lip lines and photoaged cheeks in lighter skin
- Sessions
- 1 (fractional: 1–3)
- Downtime
- 5–10 days raw and red; pink for weeks
- Cost
- €600–2,000 a fractional session; €2,500–5,000+ full-field
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Moderate evidence Non-ablative fractional lasers (1550/1540/1927 nm)
Heat without wounding: two to four sessions improve texture and fine lines with a day or two of redness; comparable to ablative in some reviews for photoaging, weaker for deep lines.
Non-ablative fractional lasers (1550/1540/1927 nm)
Heat without wounding: two to four sessions improve texture and fine lines with a day or two of redness; comparable to ablative in some reviews for photoaging, weaker for deep lines.
Heat without wounding: two to four sessions improve texture and fine lines with a day or two of redness; comparable to ablative in some reviews for photoaging, weaker for deep lines.
Non-ablative fractional lasers heat columns of dermis under an intact epidermis, so collagen remodels without an open wound. A systematic review found outcomes for photoaging statistically comparable to ablative devices with a far better tolerability profile (systematic review), and an evidence review found them safe and effective in darker skin types (review); a high-power 1540 nm device produced visible, quantifiable improvement in roughness and texture (2022 study). The honest limit: for deep, etched lines the improvement is partial and needs several sessions, and around the mouth an ablative device or a deep peel does more in one go. A good first laser for fine lines and the cheeks; the wrong one for smoker's lines.
- Best for
- fine lines and texture in someone who cannot take a week off, and in darker skin
- Sessions
- 3–4, a month apart
- Downtime
- 1–3 days of redness and swelling
- Cost
- €500–1,000 / session
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Moderate evidence Microneedling (with or without serum)
Randomised split-face trials show wrinkle and texture improvement, larger when growth factors or antioxidants are needled in; modest, safe in all skin types, four to six sessions.
Microneedling (with or without serum)
Randomised split-face trials show wrinkle and texture improvement, larger when growth factors or antioxidants are needled in; modest, safe in all skin types, four to six sessions.
Randomised split-face trials show wrinkle and texture improvement, larger when growth factors or antioxidants are needled in; modest, safe in all skin types, four to six sessions.
Microneedling punches thousands of microscopic channels that trigger a wound-healing collagen response without heat. For rejuvenation the controlled evidence is real but modest: in a randomised split-face trial, needling with topical growth factors significantly improved wrinkles and pigmentation over needling alone (RCT); a double-blinded split-face trial found a vitamin C/E/ferulic serum applied after needling improved photoaging measures over needling alone (2026 trial). Its real advantages are safety in darker skin, where lasers risk pigment, and the ability to deliver actives past the barrier — the same reason vitamin C serums needled in have caused granulomas (case series), so only sterile, purpose-made products go on an open face. Our microneedling guide covers depths, devices and the RF versions.
- Best for
- fine lines and texture in darker skin, or as the delivery route for serums
- Sessions
- 4–6, a month apart
- Downtime
- 1–2 days of redness
- Cost
- €150–300 / session
Available at a partner clinic
EGP Aesthetics — Microneedling Facial (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £200, 90 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Medium-depth TCA peels
A systematic review and a randomised trial in postmenopausal women show improvement in fine and deep wrinkles and dyschromia; a week of peeling, the cheapest resurfacing there is.
Medium-depth TCA peels
A systematic review and a randomised trial in postmenopausal women show improvement in fine and deep wrinkles and dyschromia; a week of peeling, the cheapest resurfacing there is.
A systematic review and a randomised trial in postmenopausal women show improvement in fine and deep wrinkles and dyschromia; a week of peeling, the cheapest resurfacing there is.
Trichloroacetic acid at 25–35%, usually after a Jessner's or glycolic prime (the Monheit combination), coagulates the epidermis and upper dermis and provokes a healing response that thickens the dermis and reorganises collagen. A systematic review found TCA peeling significantly improves photoaged facial skin, with medium-depth peels effective for wrinkles (systematic review), and a randomised study in postmenopausal women showed improvement in fine and deep wrinkles, dyschromia and global assessment (2025 trial). Cheaper than a laser and nearly as effective for fine lines in the right hands; more depth-dependent on the operator, and a pigment risk in darker skin. Our peel guide grades every depth.
- Best for
- fine lines and mottled photoaging on a budget, in lighter skin
- Sessions
- 1–2 a year
- Downtime
- 5–7 days of peeling
- Cost
- €300–800
Available at a partner clinic
EGP Aesthetics — Medical Skin Peel (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab), from £200, 45 min. A nurse-led clinic in London, United Kingdom; the first consultation is free.
Book this treatment (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) Or book a free consultation first, or see all clinics for this guide.
Moderate evidence Phenol–croton oil peel (deep)
The most powerful non-surgical wrinkle treatment, especially for lip lines — decades of series and surgeons’ consensus, no randomised trial, about ten days of raw skin, cardiac monitoring and permanent lightening.
Phenol–croton oil peel (deep)
The most powerful non-surgical wrinkle treatment, especially for lip lines — decades of series and surgeons’ consensus, no randomised trial, about ten days of raw skin, cardiac monitoring and permanent lightening.
The most powerful non-surgical wrinkle treatment, especially for lip lines — decades of series and surgeons’ consensus, no randomised trial, about ten days of raw skin, cardiac monitoring and permanent lightening.
A phenol peel with croton oil reaches the mid-dermis, and the depth is set by the croton-oil concentration rather than the phenol (Hetter's work). Nothing else non-surgical removes deep perioral and periorbital lines as completely, and the result lasts a decade; segmental peels of just the lip or eye zone are common, and the combination of a facelift with a perioral phenol peel is well documented (outcomes study; JAAD review). The evidence is surgeons' series and consensus, never a randomised trial, which caps it at moderate despite its power.
The price: phenol is absorbed and cardiotoxic, so full-face peels are done in stages with cardiac monitoring — done properly, no clinically significant arrhythmias occurred in a large series (study), but a fatal case has been analysed in the literature (forensic report); the treated skin is permanently lighter, so it suits fair skin and a full-face or clearly bordered zone. A serious tool for a serious problem, in very few hands.
- Best for
- deep perioral and periorbital lines in fair skin, when a laser has not been enough
- Sessions
- Once
- Downtime
- About 10 days raw; red for 2–3 months
- Cost
- €2,000–5,000+
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Radiofrequency microneedling (Morpheus8, Potenza)
Heat delivered by insulated needles remodels the dermis: prospective and self-controlled studies show periorbital and global wrinkle improvement, no controlled trial against plain needling or a laser, and an FDA alert on burns and fat loss.
Radiofrequency microneedling (Morpheus8, Potenza)
Heat delivered by insulated needles remodels the dermis: prospective and self-controlled studies show periorbital and global wrinkle improvement, no controlled trial against plain needling or a laser, and an FDA alert on burns and fat loss.
Heat delivered by insulated needles remodels the dermis: prospective and self-controlled studies show periorbital and global wrinkle improvement, no controlled trial against plain needling or a laser, and an FDA alert on burns and fat loss.
Radiofrequency microneedling adds bulk heating to the needle injury, and histology shows more collagen, elastin and vessels afterward. Clinically the wrinkle evidence is a stack of prospective and self-controlled studies — periorbital lines improved in a 24-person nonrandomised trial across skin types (2024 study), and static periorbital wrinkles in a self-controlled series (2024 series) — and a 2026 systematic review that finds it effective across indications while noting the absence of head-to-head randomised comparisons (systematic review). The FDA has alerted clinicians to serious complications including burns, scarring and fat loss (FDA alert) and 2026 studies describe facial fat loss after aggressive settings (Medscape). Plausible, popular, priced like a laser, and graded like a promising device.
- Sessions
- 3, 4–6 weeks apart
- Downtime
- 2–4 days
- Cost
- €400–900 / session
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Emerging evidence Monopolar radiofrequency (Thermage)
Tightens loose skin modestly in a 2025 randomised trial and a series of over 600 treatments; for wrinkles themselves the trials are registered, not published. A laxity device that gets sold for lines.
Monopolar radiofrequency (Thermage)
Tightens loose skin modestly in a 2025 randomised trial and a series of over 600 treatments; for wrinkles themselves the trials are registered, not published. A laxity device that gets sold for lines.
Tightens loose skin modestly in a 2025 randomised trial and a series of over 600 treatments; for wrinkles themselves the trials are registered, not published. A laxity device that gets sold for lines.
Monopolar radiofrequency heats the deep dermis and fat septa to contract collagen and provoke new collagen over months. For laxity there is a 2025 randomised controlled trial showing long-term tightening (RCT) and a retrospective series of over 600 treatments (series); for wrinkles as such, a facial-wrinkle trial exists only as a registration (registry). It is a reasonable buy for mild laxity in someone who refuses downtime, which is the jowls guide's territory, and a poor buy for a line, which it does not target.
- Sessions
- Once a year
- Downtime
- None
- Cost
- €1,500–3,500
Consultation at a partner clinic
EGP Aesthetics — no clinic in our directory offers this treatment yet. You can talk it through, and the alternatives, in a free consultation. A nurse-led clinic in London, United Kingdom.
Book a free consultation (opens hhgdmw-deagingeur-e5087aa6-doriansternvukotic.wix-site-host.com in a new tab) See all clinics for this guide.
Limited evidence IPL "photorejuvenation"
A randomised split-face trial found IPL improved pigmentation, vessels and texture but had no effect on wrinkles. Good for the colour of photoaging, not the lines.
IPL "photorejuvenation"
A randomised split-face trial found IPL improved pigmentation, vessels and texture but had no effect on wrinkles. Good for the colour of photoaging, not the lines.
A randomised split-face trial found IPL improved pigmentation, vessels and texture but had no effect on wrinkles. Good for the colour of photoaging, not the lines.
Intense pulsed light targets pigment and blood vessels, and that is what it fixes: in a randomised, blinded split-face trial, IPL improved pigmentation, visible vessels and texture but showed no efficacy on wrinkles (JAMA Dermatology). Because the brown and red of photoaging make a face look older, IPL often makes people look younger without changing a single line — a useful trick, honestly labelled. For the lines, see the lasers above. The laser guide covers when IPL is the right first device.
- Sessions
- 3–5
- Downtime
- None
- Cost
- €120–400 / session
The starting routine
What you can do at home
Three steps, a few minutes a day: the base every treatment builds on, and the only prevention with randomised trials behind it.
-
Morning
Sunscreen, SPF 30 or higher
Daily use meant 24% less measured skin aging over 4.5 years in 903 adults (the Nambour trial). The evidence.
Our pick
La Roche-Posay Anthelios UVMune 400 Invisible Fluid SPF50+ — the unperfumed version: a water-resistant SPF 50+ fluid from a European pharmacy brand, with Mexoryl 400 for the longest UVA rays; 50 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
-
Night, two nights a week at first
A retinoid
Tretinoin on prescription is the strongest; without one, retinal or a stabilised retinol, building up to nightly. The evidence.
Our pick
Medik8 Crystal Retinal 6 — 0.06% retinaldehyde in an encapsulated night serum — one step from retinoic acid and outside the EU retinol limit — with Crystal Retinal 10 (0.1%) as the next step up; 30 ml.
Buy at Lookfantastic (opens eu.lookfantastic.com in a new tab) Also at Care to Beauty.
-
Any time
Collagen peptides, about 10 g, with vitamin C
Pooled trials show better hydration, elasticity and wrinkle depth over 8–12 weeks. The evidence.
Our pick
Aeterna COLLAGEN MAX PRO — 10 g of Peptan® collagen peptides per 13 g scoop, with a hyaluronic-acid matrix, plant ceramides and acerola vitamin C. Bovine, or fish in the Marin C+ version.
See the product Label facts, prices, the evidence graded.
Fine lines take about twelve weeks to answer. Expression lines that stay at rest, and folds, do not answer to skincare at all: they are the next step, below. Not in pregnancy: retinoids are not for then.
The next step, proven clinical treatments
Where to have them done
Clinics that offer the treatments graded above, listed in the order of the evidence, with the clinic's own prices. A consultation first is the right first step for every treatment on this page.
Commercial note: listed clinics are partners and may pay us a referral fee when you book through our links. That has no bearing on how the evidence is graded, and clinics are ordered by the evidence, never by what they pay.
In your country
Elsewhere in Europe
Further afield
London, United Kingdom · nurse-led
EGP Aesthetics
Nurse-led aesthetic clinic in London SW8, offering advanced non-surgical and biostimulating treatments (Profhilo, polynucleotides, PRP, exosomes and Sculptra) for natural-looking results.
809 Wandsworth Road, SW8 3JH · English spoken
Interactive
Match a plan to your lines
Which wrinkles do you have? Open the one that looks like yours: first how to tell, then the plan, each link jumping to the graded section in the order to try them.
Fine lines and crepey texture on the cheeks or under the eyes
How to tell
Stretch the skin gently between two fingers. If the line disappears, it is a surface line in thinned, sun-damaged skin, and skincare and light resurfacing reach it. If a groove remains, it has reached the dermis: read the next two.
The plan
01 Tretinoin (or a stated-strength retinol) the one cream that rebuilds the upper dermis — decades of trials 02 Daily sunscreen 24% less measured aging over 4.5 years in the only randomised trial of aging itself 03 Non-ablative fractional laser texture and fine lines with a day or two of redness Lines that appear only when I frown, squint or raise my brows
How to tell
Frown, squint or raise your brows in the mirror, then relax completely. A line that shows only with the expression and is gone at rest is dynamic: the muscle folding the skin is the cause.
The plan
01 Botulinum toxin dynamic lines are its home territory — 77–89% responders at a month 02 Plus the retinoid base so the skin between doses keeps improving Lines that stay even when my face is still (etched forehead, crow’s feet)
How to tell
Make the expression, then relax. A line that stays, even faintly, is static: the skin under the crease no longer springs back, so the muscle needs stopping and the skin rebuilding.
The plan
01 Toxin first stops the folding so the dermis can recover 02 Then resurfacing an ablative fractional laser rebuilds the floor of an etched line 03 A thin filler for the deepest grooves in the ones that resist both Deep folds from nose to mouth or mouth to chin
How to tell
Smile in the mirror. A groove that deepens, with a soft cheek piling up above it, is a fold: the edge of a deflating, descending cheek, not a wrinkle, which is why no cream reaches it. If the whole lower face has softened, the jowls guide has the pinch test.
The plan
01 Read this first these are volume and descent, not wrinkles — and why cream fails 02 Hyaluronic-acid filler ~80% still responding at a year; reversible 03 Or a collagen stimulator slower, subtler, up to 25 months Vertical lip lines
How to tell
Vertical lines above the upper lip that deepen when you purse your lips: etched by the pursing muscle, by sun on thin skin and by lost lip volume. Women get them earlier and worse than men, and smokers worst of all.
The plan
01 Why they are the hardest lines thin skin, a pursing muscle, sun and lost volume 02 Fractional ablative laser rebuilds the dermis where creams cannot reach 03 Or a phenol–croton oil peel the most powerful single treatment for this zone, in fair skin 04 Plus a little toxin and thin filler for the pursing and the deepest grooves Creases from sleeping, or lines on my chest
How to tell
Lines on the cheek or temple, or a diagonal on the chest, that run in a different direction from your expression lines: pillow pressure makes them, not a muscle.
The plan
01 Sleep wrinkles mechanical, plausible, and thinly evidenced 02 Silicone patches and back-sleeping cheap experiments; hours of effect 03 Sunscreen to the chest where the real damage is I'm in my twenties and want to prevent all of it
How to tell
Your face is smooth at rest, and lines show only with expression, if at all. Nothing needs treating yet; what you do now decides how much there is to treat later.
The plan
01 Prevention in numbers the only randomised prevention evidence costs €20 a month 02 A retinoid from the late twenties the dermatologist consensus, and the trials behind it 03 "Baby Botox" — read before buying one pair of twins is the evidenceIn more detail
Fine lines and crepey texture
Fine lines and crepey texture
Fine lines are the crinkle you see on the cheek, under the eye and on the chest when the skin is relaxed: shallow, multidirectional, and gone the moment you gently stretch the skin between two fingers. They are the epidermis and upper dermis after years of UV — thinner, drier, with fragmented elastic fibres — and they are the one wrinkle type skincare genuinely treats. Tretinoin thickens the epidermis and rebuilds upper-dermal collagen over months; glycolic and lactic acids smooth the surface; hyaluronic-acid serums plump it for hours.
The test: stretch it. If the line disappears, it is surface and the home tier applies. If a groove remains, it has reached the dermis and you are reading the next drawer.
Expression lines — dynamic, then static
Expression lines — dynamic, then static
The glabellar "11", crow's feet and horizontal forehead lines are made by muscles — corrugator, orbicularis oculi, frontalis — folding the same strip of skin thousands of times a day. Early on they are dynamic: visible when you frown or squint, gone when you relax. With time and sun the dermis under the crease loses the ability to recover, and the line is there at rest: static. That transition is the treatment window. Botulinum toxin stops the folding, which both erases dynamic lines and, used regularly, lets a static line soften as the dermis recovers — but a deep static line may also need resurfacing or a thin filler.
The test: make the expression in the mirror, then relax completely. A line that appears only with the expression is dynamic. A line that stays, even faintly, is static and needs the muscle stopped and the skin treated.
Folds — nasolabial, marionette, and why cream fails
Folds — nasolabial, marionette, and why cream fails
The nasolabial fold and the marionette line are made below the skin. Facial fat sits in compartments that deflate and slide downward with age while the underlying bone recedes; the skin at the fold is held by ligaments, so the cheek above it piles up against a fixed edge (Mendelson & Wong). No topical reaches that layer, and a laser only smooths the skin on top of it.
Filler works here because it replaces what was lost, either in the fold itself or — better, in most faces — in the cheek above it, which re-supports the fold. Collagen stimulators (poly-L-lactic acid) do it more slowly and for longer. When the fold is part of a general softening of the lower face, you are reading our jowls guide.
Lip lines ('smoker's lines')
Lip lines ('smoker's lines')
Perioral lines are the ones women resent most and the ones that respond least to creams. They are etched by the pursing orbicularis oris (straws, cigarettes, speech), by sun on a strip of skin with very few oil glands, and by the loss of lip volume that leaves the skin above it slack. Women get them earlier and worse than men, and smokers worst of all (JAAD, 2016).
Because the lines are deep in thin skin, the tools that work are the ones that rebuild the dermis — a fractional or fully ablative laser, or a phenol–croton oil peel, which remains the most powerful single treatment for this zone — with a few units of toxin to stop the pursing and a thin filler to lift the deepest grooves. Tretinoin helps at the margins and prevents the next ones.
Sleep creases and chest lines
Sleep creases and chest lines
Side and stomach sleeping press the face against the pillow for a third of your life, and surgeons argue that the compression and shear create "sleep wrinkles" — vertical lines on the cheek and temple, a diagonal on the chest — that differ from expression lines in direction (Aesthetic Surgery Journal, 2016). One study of sleep-side preference found no correlation with perceived facial aging, so the effect is plausible rather than proven (2013 study). Back-sleeping and a silicone chest patch are cheap experiments; nothing here is a treatment for the lines you already have.
How to read your own face (the stretch test)
How to read your own face (the stretch test)
A dermatologist reads a face in about a minute, and you can do most of it in a mirror. Stretch the skin gently between two fingers: a line that disappears is a surface line, and skincare or light resurfacing is its tier. Make the expression — frown, squint, raise the brows — and relax: a line that appears only with the expression is dynamic and belongs to toxin; a line that persists faintly at rest is static and needs the muscle stopped and the dermis rebuilt. A groove that deepens when you smile, with a soft cheek piling up above it, is a fold and belongs to filler or a collagen stimulator.
Photograph the face relaxed, in the same light, before you start anything. Dermatologists also grade photoaging on the Glogau scale (I: no wrinkles, to IV: wrinkles at rest everywhere), which is really a map of how much sun the skin has had. And take the pinch test to the lower face before deciding a fold is a wrinkle — our jowls guide explains it.
Menopause and the collagen cliff
Menopause and the collagen cliff
Estrogen keeps the dermis thick, hydrated and rich in collagen. When it falls, skin collagen declines steeply — the classic studies found the loss tracks years since menopause rather than calendar age, with the steepest fall in the first five years (1987 study; "Estrogens and aging skin"). That is why many women feel their face changed in eighteen months.
What helps is unglamorous: tretinoin (the trials include women well past 55), daily sunscreen, a barrier-repairing moisturiser, and resurfacing where the skin is already etched. Systemic hormone therapy thickens skin a little in some studies but is a decision about hot flushes, sleep and bone, not wrinkles; our 50s guide covers that evidence in full.
The action plan
The plan, month by month
What happens in which order — and when it is fair to judge it. The base comes first, whatever else you add.
Week 0: read your face and photograph it
The stretch test sorts surface lines from etched ones from folds; same-light photos are the only honest judge.
Weeks 1–8: the retinoid ramp
Two or three nights a week, buffered; dryness peaks at week three and passes. Most people quit here — don’t.
Months 3–6: first change
Fine lines soften and texture evens; toxin, if you added it, has peaked and faded once by now.
Month 6–12: add the next rung
Toxin for what still moves, filler for what has folded, resurfacing for what is etched — never skipping the base.
Frequently asked questions
Retinol or tretinoin?
Tretinoin, if you can
Retinol or tretinoin?
Tretinoin, if you can
Tretinoin has the randomised trials, the meta-analysis and the biopsies; retinol has weaker but real data and far better tolerance, and a well-made retinol regimen approached tretinoin in a split-face comparison. If you can get tretinoin (prescription-only in the EU and UK; sold over the counter in some countries elsewhere), start low and slow. If you cannot, or your skin rebels, a stated-percentage retinol or retinaldehyde is the next best thing and still ahead of every peptide, snail and stem-cell cream.
When should I start?
SPF now; retinoid late 20s
When should I start?
SPF now; retinoid late 20s
Prevention has no minimum age — the sunscreen trial enrolled adults under 55 and showed benefit across the range. A retinoid from the late twenties is where the dermatologist consensus sits, because that is when collagen turnover starts to lose. Toxin is warranted when an expression line begins to persist after the expression ends, whenever that is; a smooth face at rest does not need it. Filler is for a fold you can see, and the 30s guide explains why early filler is a subscription with MRI evidence of persistence.
How long until I see something?
Hours to 12 weeks
How long until I see something?
Hours to 12 weeks
The timeline is the tell for what a product is doing. Anything that changes a line in hours is hydrating the surface and will be gone tomorrow. Toxin takes three to five days to start and two weeks to peak. Retinoids, vitamin C, niacinamide and acids change the dermis, which turns over slowly: the trials ran 12–24 weeks, and improvement continued to a year. After a laser or peel the skin looks worse for a week, better at a month, and best at three as new collagen matures. Photograph in the same light at the same time of day, or the mirror will lie to you both ways.
If I stop toxin, will the lines come back worse?
No
If I stop toxin, will the lines come back worse?
No
The muscle recovers fully within three to four months and the skin is no worse for the interruption; the myth of rebound comes from comparing a treated face with its untreated self after a long gap. If anything, the years the crease was not being folded give the dermis time to recover, which is why long-term users often need less. Stopping is safe at any point.
Why does my expensive cream do nothing for the lines from my nose to my mouth?
Folds need filler
Why does my expensive cream do nothing for the lines from my nose to my mouth?
Folds need filler
The nasolabial fold is where a deflating, descending cheek meets skin tethered by a ligament; the skin over it may be perfectly healthy. Skincare improves the skin's surface and does nothing to the volume beneath, which is why people spend a decade on creams for a line that a syringe would soften in ten minutes. See the folds drawer above and the filler guide; if the fold is part of a general lower-face softening, the jowls guide.
Do I need an eye cream?
No
Do I need an eye cream?
No
The skin under the eyes is thinner and the actives are the same; there is no ingredient that works only in an eye cream. Use a lower-strength retinoid a few nights a week close to (not on) the lid margin, sunscreen to the orbital rim, and a moisturiser. Crow's feet are expression lines and belong to toxin; under-eye hollows are volume and belong, cautiously, to filler; puffiness is fat and fluid, not skin. The 30s guide has the eye-cream evidence in full.
What actually works on lip lines?
Resurfacing + toxin
What actually works on lip lines?
Resurfacing + toxin
Lip lines are deep, in thin skin, driven by muscle, sun and lost volume, so they need the whole toolkit. The dermis is rebuilt with a fractional ablative laser or, for the deepest lines in fair skin, a phenol–croton oil peel; the pursing is quietened with two to four units of toxin per side; the deepest grooves and the deflated lip border get a thin hyaluronic-acid gel. Tretinoin and sunscreen keep the next ones away. Skincare alone will disappoint here, and so will filler alone, which makes the lip look stuffed while the lines stay.
Are collagen drinks worth it?
Modestly
Are collagen drinks worth it?
Modestly
The pooled trials show real but small improvements in hydration, elasticity and wrinkle depth over 8–12 weeks; the 2025 meta-analysis that found none in the independently funded trials leaned on low doses and forearm skin (see the collagen row). Take about 10 g a day with vitamin C: drinks and gummies with a gram or two may not be enough. If you enjoy it and can afford €30 a month, it is a reasonable add-on; if you are choosing between it and tretinoin, the choice is not close, and the two work best together. The collagen guide covers forms, doses and the vegan question.
Silk pillowcases and back-sleeping?
Plausible, cheap
Silk pillowcases and back-sleeping?
Plausible, cheap
The surgeons' argument for sleep wrinkles is mechanical and reasonable, and one study found no link between sleep side and facial aging, so the honest answer is "probably a little". Sleeping on your back removes the pillow from the equation; a silk or satin pillowcase reduces friction and the morning creases; a silicone chest patch is the same idea for the décolletage. None of them costs anything to try and none of them treats what is already there.
What is the cheapest thing that works, and the most effective?
€20 / month to €5,000
What is the cheapest thing that works, and the most effective?
€20 / month to €5,000
The ladder in euros: sunscreen and tretinoin (€20–50 a month, the only prevention with trials) → niacinamide, vitamin C, acids (€10–80, modest) → toxin (€200–400 an area, three to four months) → filler (€300–600 a syringe, a year) → non-ablative laser, peels, needling (€150–1,000 a session, several sessions) → ablative laser or deep peel (€600–5,000+, years). Each rung does something the one below cannot, and none of the upper rungs replaces the bottom one. Most faces over 40 that look expensive are running the whole ladder; most that look good in their thirties are running the first rung.
Safety
A retinoid stings and flakes for the first weeks, and that settles. Toxin and filler are medical procedures: choose an injector who can manage what goes wrong.
Retinoids: the irritation curve, the sun, and pregnancy
Six to eight weeks of dryness is normal and passes; sunscreen is mandatory; tretinoin and adapalene are avoided in pregnancy and breastfeeding, bakuchiol is the substitute.
Retinoids: the irritation curve, the sun, and pregnancy
Six to eight weeks of dryness is normal and passes; sunscreen is mandatory; tretinoin and adapalene are avoided in pregnancy and breastfeeding, bakuchiol is the substitute.
The irritation curve. Redness, dryness and flaking peak at two to four weeks and settle by eight; the fix is a lower strength, fewer nights, a moisturiser buffer and patience — not stopping. Avoid the eyelids and the corners of the nose and mouth at first.
Sun. Retinoids thin the dead surface layer, so new users burn a little more easily in the first weeks, and sunlight breaks the molecule down — apply at night; daily sunscreen is part of the prescription, not an add-on.
Pregnancy. Topical tretinoin and adapalene are avoided throughout pregnancy and breastfeeding as a precaution (oral isotretinoin is a proven teratogen; the topicals are not, but nobody tests it). Bakuchiol, vitamin C, niacinamide, azelaic acid and glycolic acid are the pregnancy-safe alternatives.
Procedures. Stop retinoids about a week before peels, lasers and waxing, and resume once the skin has healed.
Botulinum toxin: droop, spread, and who holds the syringe
Eyelid or brow droop in a few percent, temporary; heavy brows from over-treated foreheads; rare antibody resistance; not in pregnancy or with certain neuromuscular diseases; only licensed products from licensed injectors.
Botulinum toxin: droop, spread, and who holds the syringe
Eyelid or brow droop in a few percent, temporary; heavy brows from over-treated foreheads; rare antibody resistance; not in pregnancy or with certain neuromuscular diseases; only licensed products from licensed injectors.
Cosmetic toxin has one of the cleanest safety records in medicine at the doses used, and the problems are almost all placement. Eyelid ptosis (toxin drifting into the eyelid muscle) affects a few percent, lasts weeks and is treatable with apraclonidine drops; a "heavy" brow comes from over-treating the forehead in someone whose frontalis is holding the brows up; asymmetry is a touch-up. Headache and bruising are common and trivial. Antibody resistance is rare and linked to frequent high doses. It is avoided in pregnancy and breastfeeding and in myasthenia and similar conditions, and it interacts with aminoglycoside antibiotics.
The real hazard in Europe is the market: grey-import and counterfeit toxins, "toxin parties", and injectors with a weekend certificate. Licensed product (the box has a batch number you can ask to see), a clinician who examines your muscles before choosing sites, and a follow-up at two weeks are the whole checklist.
Fillers: vascular occlusion, blindness, nodules, overfill
Occlusion about 1 in 6,400 needle syringes and 1 in 41,000 by cannula; 511 published blindness cases worldwide; delayed nodules under 5%; the commonest harm is the overfilled face. HA is reversible, the others are not.
Fillers: vascular occlusion, blindness, nodules, overfill
Occlusion about 1 in 6,400 needle syringes and 1 in 41,000 by cannula; 511 published blindness cases worldwide; delayed nodules under 5%; the commonest harm is the overfilled face. HA is reversible, the others are not.
Vascular occlusion — filler entering an artery — is the emergency: skin necrosis or, if it reaches the eye's circulation, blindness. A large practitioner survey puts the rate at about 1 occlusion per 6,410 syringes by needle and 1 per 40,882 by cannula (survey analysis); 511 cases of filler-related blindness have been published worldwide, mostly from the nose, glabella and forehead (2024 review); with hyaluronidase given fast, 84% of pooled HA occlusions recover at least partly (pooled analysis). Your injector must stock hyaluronidase and know the protocol.
Nodules and delayed reactions occur in a fraction of a percent to a few percent, sometimes months later and sometimes after infections or vaccines; most resolve with hyaluronidase or steroids (review). Overfill — the puffy, front-heavy "pillow face" from years of topping up gel that never fully left — is the commonest harm and the one nobody counts (facial overfilled syndrome). HA dissolves; poly-L-lactic acid and calcium hydroxylapatite do not, which is the argument for starting with HA.
Lasers and peels: pigment, scars, cold sores, and phenol
Delayed hypopigmentation after full ablation (~8%), post-inflammatory darkening in darker skin, scarring on the neck and with infection, herpes reactivation without prophylaxis, and cardiac monitoring for phenol.
Lasers and peels: pigment, scars, cold sores, and phenol
Delayed hypopigmentation after full ablation (~8%), post-inflammatory darkening in darker skin, scarring on the neck and with infection, herpes reactivation without prophylaxis, and cardiac monitoring for phenol.
Pigment. The two-sided risk of resurfacing: darker skin (Fitzpatrick IV–VI) darkens after injury — post-inflammatory hyperpigmentation in about 4% of sessions even with a non-ablative laser and careful settings (series) — while aggressive full-field CO₂ produced delayed permanent lightening in about 8% of fair patients (1999 series). Test spots, conservative settings, pre- and post-treatment pigment control and strict sun avoidance are the answer; so is choosing non-ablative or needling in darker skin.
Scarring and infection. Hypertrophic scars follow over-treatment, especially on the neck and jawline (neck scarring after fractional CO₂), and any infection of a resurfaced face — bacterial, yeast, or herpes — can scar. Antiviral prophylaxis brings herpes reactivation to near zero (study) and is standard for anything ablative or a medium peel.
Phenol. Absorbed phenol can trigger arrhythmias; deep peels are done in stages with cardiac monitoring and hydration, and only by people who do them often (monitored series; fatal case). Isotretinoin no longer means a six-month wait for everything: two 2017 US consensus papers found no reason to delay superficial peels or non-ablative and fractional lasers, and advise against only fully ablative resurfacing and mechanical dermabrasion (Waldman 2017; Spring 2017); the Indian guidelines also clear medium peels and microneedling, but keep the six-month wait for deep peels, dermabrasion and full-face ablative CO₂ (Mysore 2017).
Hyaluron pens, home lasers, and imported toxin
Needle-free "hyaluron pens" have caused occlusions and infections and are warned against by regulators; home lasers are too weak to matter; imported toxin and filler have no batch control.
Hyaluron pens, home lasers, and imported toxin
Needle-free "hyaluron pens" have caused occlusions and infections and are warned against by regulators; home lasers are too weak to matter; imported toxin and filler have no batch control.
Three things marketed straight to consumers deserve a flat no. Needle-free "hyaluron pens" fire filler into the skin at high pressure with no control over depth or vessel, and have caused vascular occlusions, infections and permanent lumps; regulators in several countries have warned against them. Home "laser" and radiofrequency devices are regulated to be too weak to injure, which also makes them too weak to treat a wrinkle — the manufacturer-run studies show minor, temporary changes. And toxin or filler bought online for self- or salon injection has no supply chain: counterfeit, degraded or bacterially contaminated product is the norm in seizures. The cheapest legitimate option on this page is a tube of tretinoin; the cheapest illegitimate one can cost an eye.
Educational content, not medical advice. Retinoids are avoided in pregnancy; injectables and resurfacing carry rare but serious risks that depend on who performs them — see the safety drawers and choose a licensed clinician who examines your face before quoting a treatment.